
Childhood health is not only a matter of individual wellbeing; it can shape how much children learn, what skills they develop, and how productively they participate in the economy as adults.
The Minneapolis Federal Reserve article summarized here examines that long horizon through a central public-policy question: can health coverage in childhood contribute to later economic growth?
The issue is especially significant in the United States, where Medicaid covers a large share of children and births, while public health programs represent a substantial portion of national economic activity.
On This Page
- Childhood health and the foundations of economic growth
- Medicaid’s reach and role in childhood coverage
- How researchers assess effects over a lifetime
- Public health spending and the economic accounting question
- What the evidence can mean for policy decisions
- The central message: childhood coverage is an economic question too
The source connects this modern safety net to historical evidence that illness can hinder children’s development and hold back communities, including the impact of hookworm in the southern United States.
Rather than treating health spending as either a cost or a guaranteed investment, the analysis asks what the evidence can establish. Medicaid’s reach, the mechanisms connecting health to learning and productivity, and the challenges of measuring outcomes over decades all matter when assessing whether childhood coverage has lasting economic value.
TL;DRChildhood health can influence long-run economic growth by affecting children’s ability to learn, develop skills, and become productive adults. Medicaid reaches tens of millions of children and many pregnant women, making it a major setting for examining whether health coverage changes later-life outcomes.
The source frames the question rather than supplying detailed study results: whether Medicaid coverage in childhood improves economic outcomes over time, and how those potential benefits should be weighed against the scale of public health spending.
Coverage may create the conditions for development, but the size and durability of its economic effects require careful evidence.
Childhood health and the foundations of economic growth
The central idea is that health can influence economic performance long before a person enters the workforce. Childhood illness may interrupt development and education, while better health can make it easier to attend school, concentrate, and build capabilities that matter later in life.
Health shapes the capacity to learn
Learning depends on more than school access. A child who is frequently ill may miss lessons, struggle to concentrate, or have less energy for ordinary classroom demands. Health problems can therefore affect educational progress through several connected pathways, even when schooling itself remains available.
The source uses hookworm in the southern United States as a historical illustration of this connection. The infection harmed children’s development, and the resulting damage was linked to slower regional economic progress. The example shows how health burdens can extend beyond individual households.
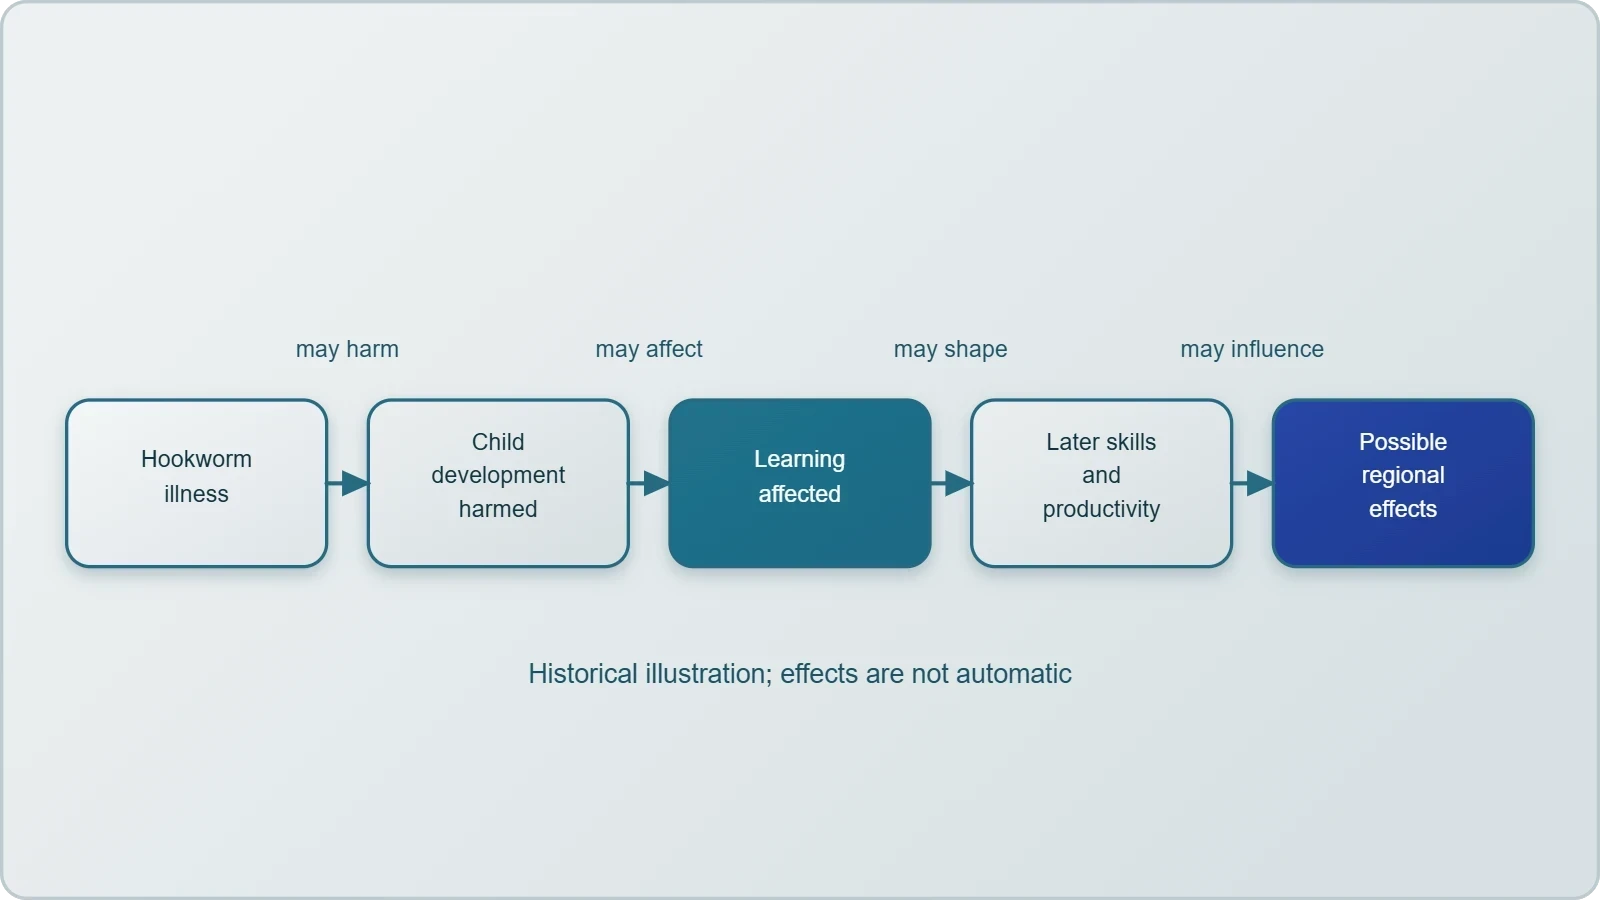
This relationship is not automatic or identical for every child. The effect of an illness can depend on its severity, duration, timing, and the resources available to families and schools. A policy analysis must distinguish plausible pathways from effects demonstrated by particular research designs.
When researchers study long-term outcomes, they are often asking whether early-life conditions leave a measurable imprint on later education, employment, or earnings. These outcomes develop over many years, so the evidence must connect childhood exposure to adult measures without overstating what a single study can prove.
Skills and productivity accumulate over time
Economic productivity reflects the skills, knowledge, health, and experience people bring to work. Childhood is an important period in which several of these capacities develop. Health can support that process by helping children participate consistently in learning and social environments.
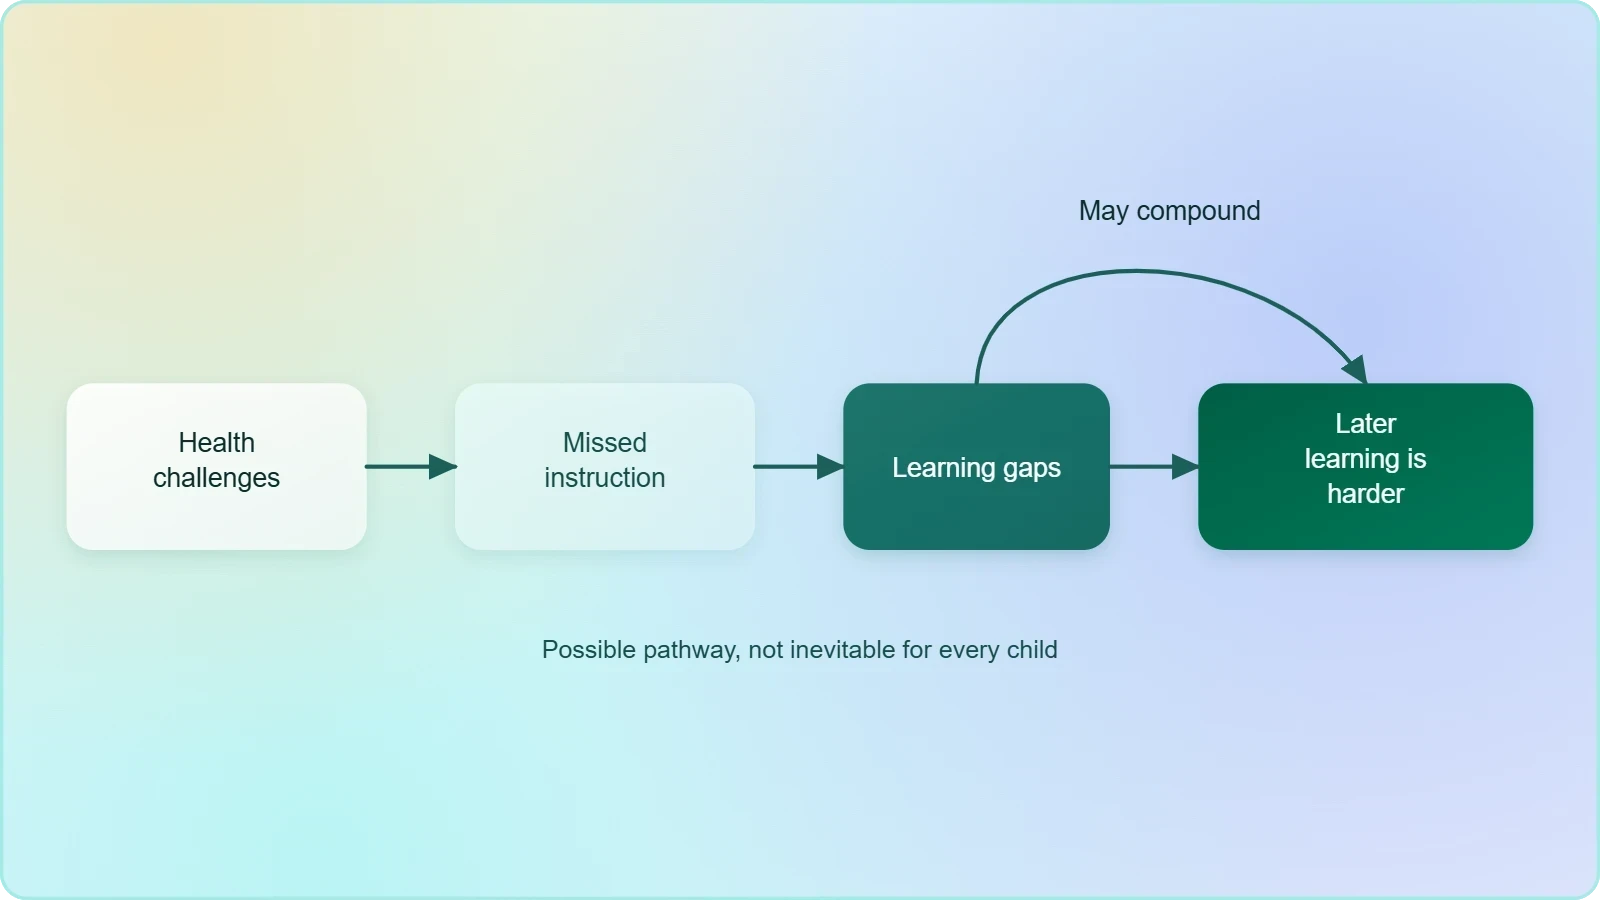
When poor health disrupts development, the consequences may compound. Missed instruction can create gaps that make later learning harder, while persistent health challenges may limit a young person’s ability to take advantage of educational opportunities. These are mechanisms to investigate, not guaranteed outcomes for every child.
The economic significance of an individual health improvement may appear modest at first, yet a population-wide effect can matter when many children experience better access to care. Whether such gains occur depends on the quality, timing, and practical availability of services, not merely insurance enrollment.
For policymakers, this broader perspective changes the question from whether a program pays for medical visits to whether it supports conditions for human development. That distinction does not settle the value of Medicaid, but it clarifies why childhood coverage may warrant evaluation beyond immediate healthcare costs.
Medicaid’s reach and role in childhood coverage
Medicaid provides the policy setting for the article’s central question. According to the source, it covers more than 35 million children and about 1.5 million pregnant women, reaching roughly 47 percent of American children and 41 percent of births.
A large program with income-based eligibility
The source describes children’s eligibility as generally based on family income. Children usually pay nothing for care, a feature that can reduce direct financial barriers for families who qualify. Eligibility and access, however, are not the same thing: coverage must translate into usable services.
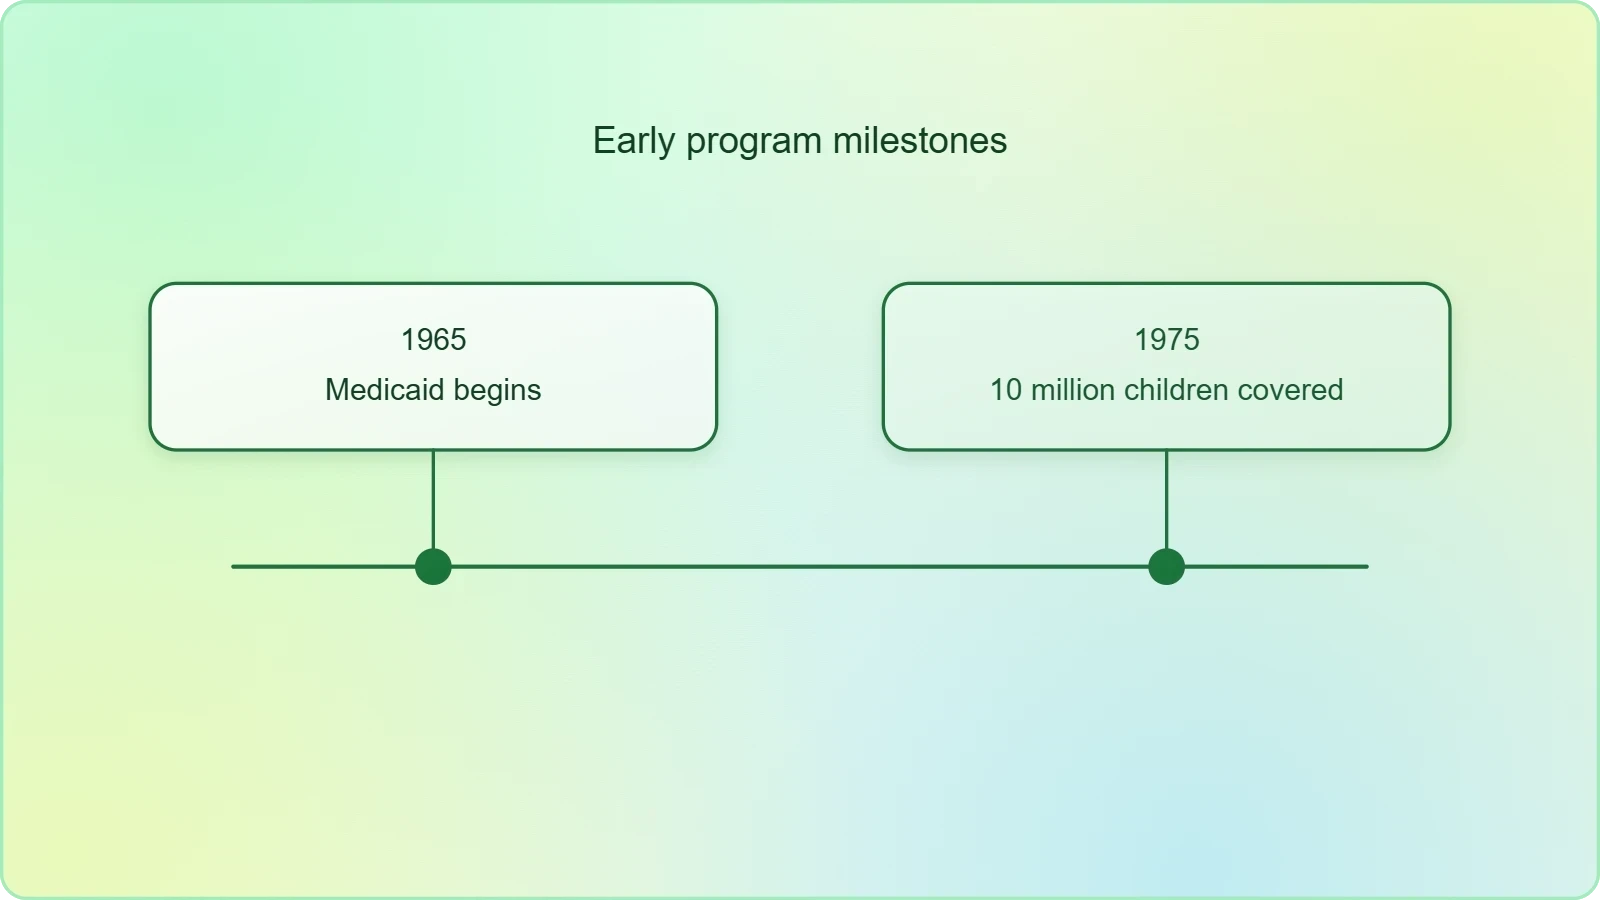
Medicaid began in 1965 and covered 10 million children by 1975, according to the supplied summary. Those milestones illustrate how the program expanded over its early years. They also provide historical context for why it now offers a broad population through which researchers can study childhood coverage.
Coverage can matter in several ways: it may make routine care more affordable, support access when health concerns arise, and reduce uncertainty about medical expenses. The source does not specify which services or mechanisms account for any observed long-term effects, so these should be treated as questions for evaluation.
A program’s scale makes its design consequential, but scale alone does not establish effectiveness. The relevant analysis must consider who qualifies, whether families can obtain care, and whether services meet children’s needs. Enrollment figures describe reach; they do not by themselves reveal developmental or economic outcomes.
Coverage is an input, not an outcome
Insurance is a financing arrangement that can facilitate access to care, but it does not guarantee that every child receives timely or suitable treatment. Availability of clinicians, local service capacity, family circumstances, and continuity of coverage can all influence whether insurance changes health in practice.
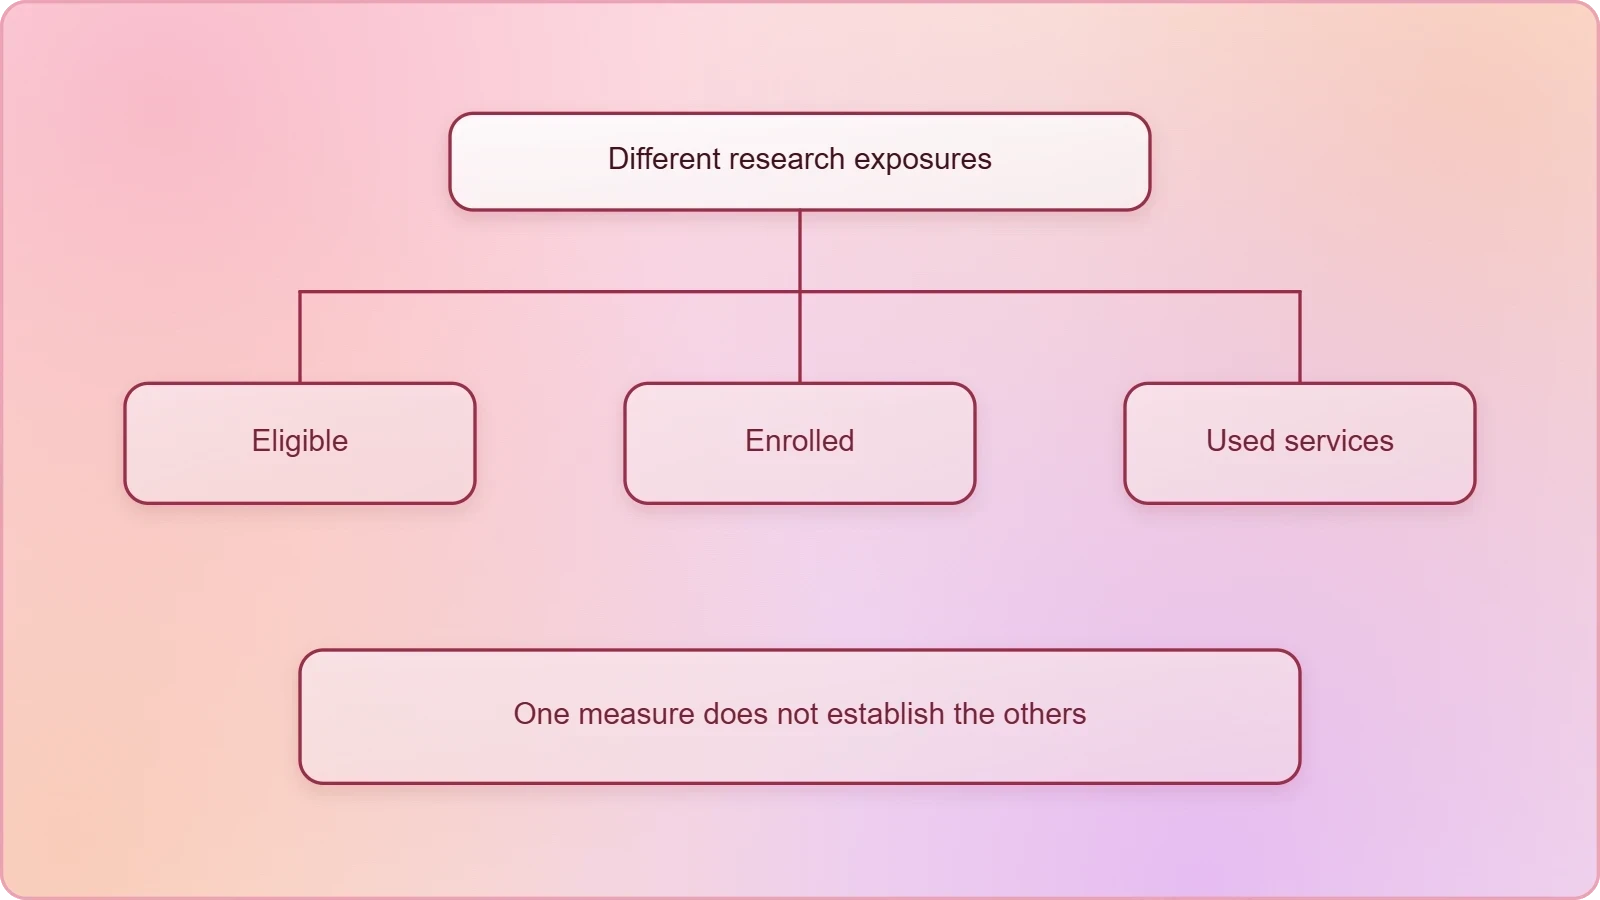
That distinction matters when interpreting research. A study may examine eligibility, enrollment, or actual use of services, and those are different exposures. Results associated with being eligible should not automatically be described as the effect of receiving a specific treatment or maintaining uninterrupted coverage.
The source’s figures show why Medicaid is economically relevant as a public program: its coverage extends across a substantial share of children and births. If health improvements influence later capabilities, a program reaching millions could have implications beyond the immediate medical system.
At the same time, the scale of coverage makes careful measurement essential. The experiences of children, families, and communities vary. An average estimate may conceal differences in access or impact, while the program’s national reach does not imply uniform effects across places and populations.
How researchers assess effects over a lifetime
The source says the Federal Reserve Bank of Minneapolis article reviews evidence on whether childhood Medicaid coverage affects later economic outcomes. This is a demanding research task because the policy exposure occurs early, while many outcomes emerge years or decades afterward.
Separating program effects from family circumstances
Children who receive public coverage may differ from children who do not in ways that also affect later outcomes. Family income, local conditions, parental health, and access to services can shape both eligibility and development. Credible evaluation must account for these differences as far as possible.
Researchers therefore need to distinguish correlation from causation. If covered children later have different outcomes, that pattern alone cannot show that Medicaid caused the difference. The central challenge is identifying a comparison that helps isolate coverage from other influences on children’s lives.
Policy changes, eligibility thresholds, or differences across groups and periods can sometimes provide useful research comparisons. The source summary does not identify the specific methods used in the article, so it would be inappropriate to attribute a particular design or numerical finding to it.
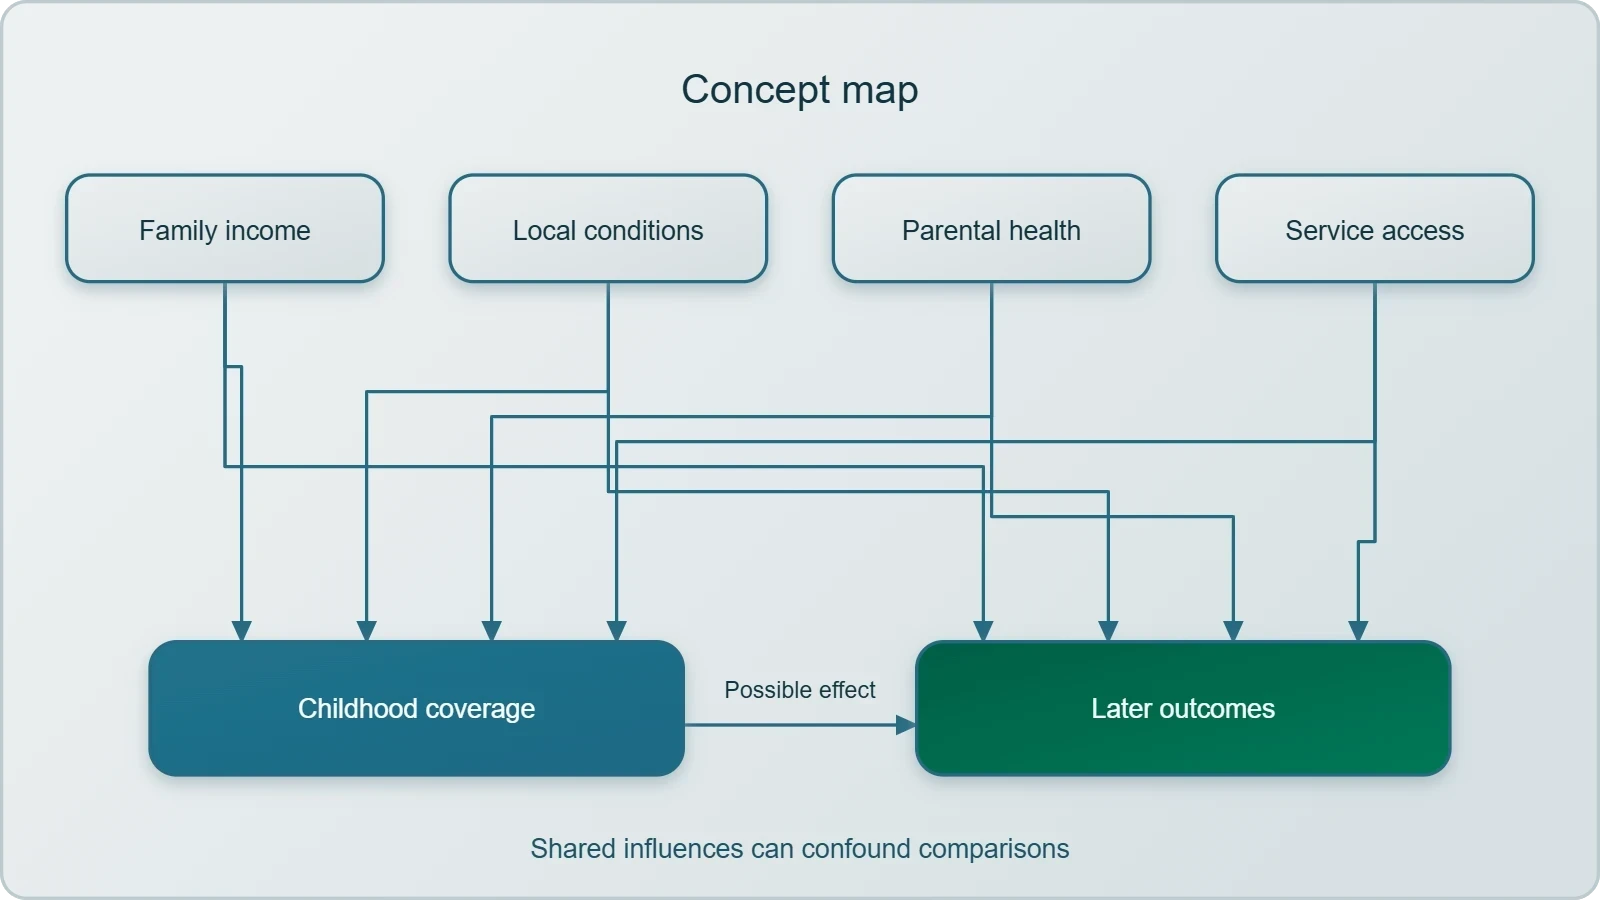
Even strong research designs have boundaries. An estimate may apply to a particular population, policy period, or form of coverage. Interpreting results carefully means describing who was studied and what changed, rather than assuming one result answers every question about Medicaid.
Choosing outcomes that capture long-term value
Economic outcomes can include educational attainment, employment, earnings, or productivity, but each measure captures a different part of adult life. A study’s conclusions depend partly on which outcomes it follows and how long it can observe the children who were covered.
Short-term measures may reveal immediate changes in healthcare access or health, while later measures can show whether early differences persist. Long follow-up is valuable but brings challenges: people move, records may be incomplete, and broader social or economic conditions change over time.
Researchers must also consider the age at which coverage occurs. Prenatal access, early childhood care, and coverage during school years may affect different stages of development. Combining these exposures into a single average could obscure when support matters most.
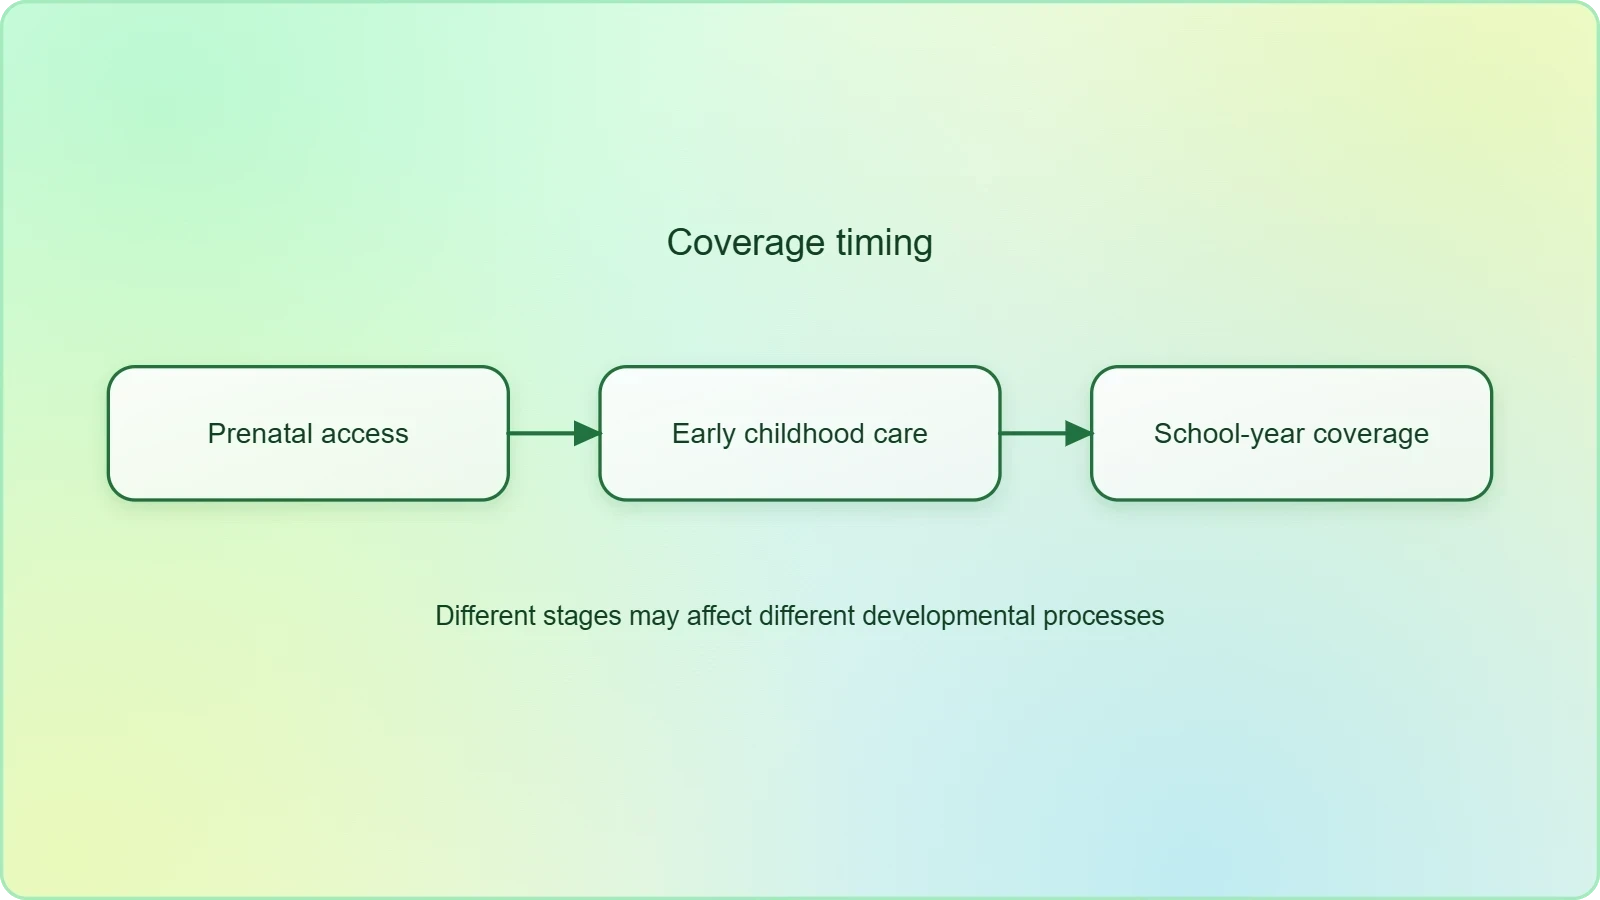
The key interpretive question is not simply whether an outcome changed, but how confidently the change can be linked to coverage and whether it is economically meaningful. The source’s framing invites this assessment without supplying detailed estimates in the summary provided.
- 01
- 02
- 03
- 04
Public health spending and the economic accounting question
The source reports that public health programs account for 8.6 percent of U.S. gross domestic product, with Medicare and Medicaid representing most of that activity. It asks whether this spending maintains health and produces economic benefits, linking public budgets to wider national performance.
Spending is not the same as economic return
Public expenditure is an input, while improved health and economic growth are possible outcomes. Treating every dollar spent as a dollar of economic gain would confuse program cost with benefit. A sound assessment must identify what changes because of the program and value those changes appropriately.
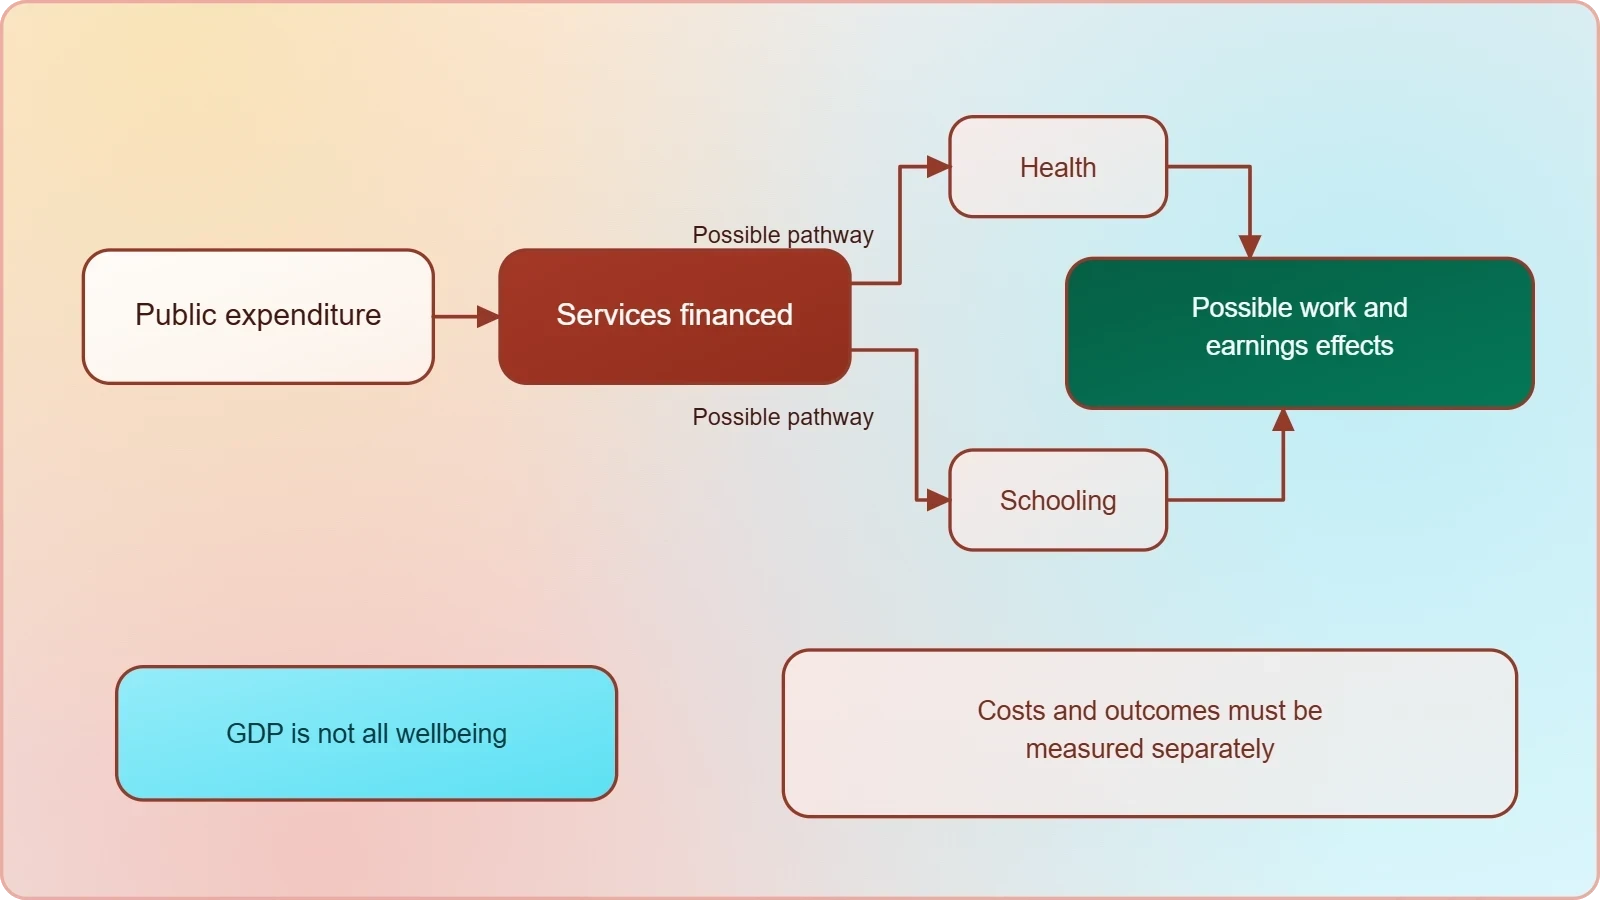
Healthcare spending may have direct effects through the services it finances and indirect effects through health, schooling, work, and family financial stability. The scale and timing of those pathways vary. The source raises the broader question but does not provide a complete cost-benefit calculation.
Gross domestic product measures the value of economic output, not every dimension of wellbeing. Health can matter intrinsically, even when its value is not fully reflected in market production. Conversely, an increase in spending does not necessarily mean that health or productivity improved.
The appropriate comparison is therefore not simply “spending versus no spending.” It is whether particular coverage arrangements improve outcomes relative to plausible alternatives, what resources they require, and which benefits are captured by families, communities, and the wider economy.
Benefits and costs may appear in different places
A childhood health program may be funded through public budgets, while some potential gains emerge later in classrooms, workplaces, or household finances. This separation across institutions and generations can make the program’s economic contribution difficult to recognize in a single annual budget.
Benefits may also be unevenly distributed. Children and families can receive more immediate value from access to care, while any later productivity effects may be diffuse. A complete policy discussion should distinguish who bears the cost, who receives the direct service, and who may gain over time.
The reported 8.6 percent GDP figure gives scale to the national health-program context, but it does not identify what proportion belongs to childhood Medicaid or how much spending yields particular outcomes. Those details would be necessary for a more specific economic appraisal.
Economic evaluation is strongest when it presents both measurable effects and uncertainty. It should avoid implying that every health improvement becomes higher earnings, while also recognizing that conventional market measures may miss developmental and social value that matters to families.
What the evidence can mean for policy decisions
The article’s policy relevance lies in connecting childhood coverage with outcomes that matter beyond the healthcare system. The question is not whether health is valuable, but how reliably public coverage can improve health and whether those changes influence later development and economic participation.
Design should support usable access
Coverage has practical value only when families can use it. Policymakers evaluating a program should consider whether eligible children are enrolled, whether care is available nearby, and whether families can maintain coverage as their circumstances change.
Program design should also be assessed against the needs of different ages and communities. Prenatal care, early childhood development, and school-age health involve distinct contexts. A broad coverage statistic cannot indicate whether services are appropriately timed or consistently accessible.
Historical examples such as hookworm underline that population health can be shaped by conditions beyond the clinic. Access to medical care is one component, alongside household resources, education, sanitation, and local infrastructure. Economic consequences may arise from the combined setting rather than insurance alone.
For this reason, an evidence-informed policy discussion should identify the specific program features under consideration. Changes in eligibility, continuity, provider access, or covered services may affect outcomes differently. General claims about Medicaid’s influence should not substitute for analysis of these policy details.
Evidence should guide proportionate conclusions
The source summary says that the article reviews evidence, but it does not state the review’s detailed conclusions or report estimates. The most responsible reading is therefore to identify the question and its significance without inventing a magnitude, claiming a settled causal effect, or assuming every child benefits in the same way.
If evidence shows later-life improvements associated with childhood coverage, interpretation should still account for the affected groups, the time period, and the outcomes measured. Policymakers need findings that are sufficiently specific to guide decisions rather than broad assurances that spending necessarily generates growth.
If effects appear limited or uncertain, that does not mean childhood health coverage has no value. Some benefits may not be captured by employment or income measures, while weak estimates may reflect study constraints. But uncertainty should be stated clearly rather than converted into a claim of proven economic return.
A balanced judgment weighs credible health and developmental outcomes alongside program costs, access conditions, and alternative uses of public resources. That approach treats Medicaid neither as an unquestionable investment nor merely as expenditure, but as a policy whose results should be tested and improved.
The central message: childhood coverage is an economic question too
The source’s core message is that child health belongs in discussions of long-term economic growth. Illness can disrupt development and learning, while access to healthcare may help preserve the conditions in which children build capabilities. Medicaid’s reach makes the question significant at national scale.
Program reach makes evaluation consequential
With more than 35 million children covered and about 47 percent of American children represented in the supplied figures, Medicaid is not a marginal policy. Its scale makes it important to understand whether coverage influences health and later outcomes, while also making careful evaluation more consequential.
The program’s history, from its establishment in 1965 to coverage of 10 million children by 1975, underscores an enduring public role. These milestones establish context, not proof of economic impact. Historical expansion should be distinguished from evidence about the effects of coverage.
The source also places Medicaid within a wider public health financing landscape, reporting that such programs account for 8.6 percent of GDP. This figure emphasizes the magnitude of public involvement, but it cannot alone tell readers whether spending is efficient or what outcomes childhood coverage produces.
For a full interpretation, readers need both sides of the analysis: what public coverage costs and what it changes. Health, education, and adult economic participation may be linked, but the strength of each link must be established through evidence rather than assumed from the program’s size.
Interpret the question without overstating the answer
The historical hookworm example provides an intuitive illustration of how a health burden can damage development and slow a region’s economy. It helps explain why health may matter for growth, while remaining distinct from direct evidence about modern Medicaid or its specific effects.
The article’s research question is therefore both practical and methodological: does childhood Medicaid coverage alter economic outcomes later in life, and how should those outcomes be weighed against the public resources involved? A useful answer requires long-term data, credible comparisons, and transparent limits.
For families, the immediate importance of coverage is access to care and protection from direct costs, as reflected in the source’s description of children’s eligibility. For policymakers, the wider concern is whether those supports also influence the health and capabilities that shape adult opportunity.
Ultimately, childhood health programs should be assessed as both health policy and potential investments in human development. The source invites that broader perspective without reducing children’s wellbeing to economic output or claiming a return that its summary does not document.
From our network :
- Committed Mediterranean Precipitation Decline: Why Emissions Cuts Alone Cannot Restore Winter RainsNew NOAA research reveals that Mediterranean winter rains may decline irreversibly even with emissions cuts. Explore the science of committed climate change and regional impacts.
- CISA’s Ten-Advisory Wave: Why Generic Patching Fails in OT and How to Build Product-Specific PlaybooksCISA released ten ICS advisories in one week, exposing critical infrastructure risks. Generic patching fails in OT. Learn to build product-specific remediation playbooks.
- Forbidden Matrix Patterns and Visible Lattice Points: A Geometric DictionaryExplore how multidimensional 0–1 matrices encode geometric truths, linking forbidden patterns to visible lattice points and hypergraph theory, with applications in combinatorics and computational geometry.
- How AI Agents Will Change the Way We Manage Personal FinancesExplore how AI agents are transforming personal finance through automated budgeting, bill payment, and investment management, while examining the critical security protocols and governance frameworks required for safe deployment.
- University Language Proficiency Exams: Why Institutional Tests Demand Different Preparation Than IELTS and TOEFLDiscover why university-specific language proficiency examinations differ fundamentally from IELTS and TOEFL, and learn strategic preparation approaches for institutional assessment success.
- The Hidden Cost of AI Convenience: Why Over-Permissioned Agents Are a Security Time BombDiscover why AI agents with excessive permissions create dangerous single points of failure, and learn how implementing least privilege principles can protect your organization from exploitation.
- The Final Descent: How ESA Retired the Legendary Cluster Constellation After 24 Years of Space Weather ScienceAfter 24 years mapping Earth’s magnetosphere, ESA’s Cluster mission concluded with a precisely controlled reentry over the South Pacific. This analysis explores the scientific legacy, engineering decisions, and debris mitigation principles behind one of space exploration’s most responsible retirements.
- Live Online English Classes for Kids: Do They Actually Reduce Anxiety?A ten-week study reveals that synchronous online English classes can significantly reduce child language anxiety while improving listening and reading skills. Discover what makes these programs effective and how parents can select the right one.
- Mobile Learning and VR in English: What Global Evidence Reveals About Effective Language TechnologyA systematic review across 14 countries reveals which language-learning technologies genuinely work. Mobile learning, AI, and VR show measurable benefits when pedagogically integrated. This evidence-based guide helps educators and learners select technology that delivers real return on investment.
RESOURCES
- Long-Term Impacts of Childhood Medicaid Expansions on ...academic.oup.comTurning to economic outcomes, females with more years of Medicaid eligibility during childhood have higher wage income starting at age 23, and the increases…
- Medicaid at 50: Covering Children Has Long-Term Educational ...cbpp.orgJul 7, 2015 ... ... economic growth that stems from the creation of a more skilled workforce. The study evaluated those born from 1980…
- Exploring the Effects of Medicaid During Childhood on the Economy ...cbo.govNov 1, 2023 ... On a present-value basis, CBO estimates that long-term fiscal effects of Medicaid spending on children could offset half or more…
- Medicaid Implementation, Adult Health, and Labor Market Outcomesnber.orgDec 1, 2016 ... Economic Fluctuations and Growth ... Published Versions. Andrew Goodman-Bacon, 2021. "The Long-Run Effects of Childhood Insurance Coverage: ...
- Long-Run Budgetary Effects of the President's 2025 Budget Proposalcbo.govDec 11, 2024 ... CBO estimates how expanding certain children's eligibility for Medicaid or the Children's Health Insurance Program over the next 10 years ...
- Medicaid as an Investment in Children: What is the Long-Term ...nber.orgFounded in 1920, the NBER is a private, non-profit, non-partisan organization dedicated to conducting economic research and to disseminating research ...
- Short-Term Medicaid Cuts, Long-Term Harm | Commonwealth Fundcommonwealthfund.orgDec 8, 2020 ... ... economic outcomes for low-income children later in life. It is well documented that both higher income and greater educational…
- The Long-Term Impacts of Medicaid Exposure in Early Childhoodpmc.ncbi.nlm.nih.govThis paper examines the long-term impact of exposure to Medicaid in early childhood on adult health and economic status ... growth trends were poor…
- The long-term impacts of Medicaid exposure in early childhoodsciencedirect.comThis paper examines the long-term impact of exposure to Medicaid in early childhood on adult health and economic status. The staggered timing of Medicaid's ...
- Medicaid: The Health and Economic Benefits of Expanding Eligibilityaspe.hhs.govSep 1, 2024 ... Long-Term Impacts of Childhood Medicaid Expansions on Outcomes in Adulthood. ... Paying for Medicaid – State Budgets and the Case…
- Medicaid at 50: A Look at the Long-Term Benefits of Childhood ...ccf.georgetown.eduJul 1, 2015 ... Medicaid's Implications for Economic Growth and. Financial Security ... 35 Two new studies find that childhood Medicaid eligibility leads to.
- How Do Children and Society Benefit from Public Investments in ...urban.orgSep 4, 2024 ... ... short- and long-term benefits of housing programs on a child's development. Short-Term Housing Outcomes. Cash assistance and income supports ...
- Yale Economics Study Finds Long-Term Impacts of Medicaideconomics.yale.eduJan 20, 2015 ... The study examines recent tax returns for almost all children born in the United States from 1981-1984, numbering approximately 10…
- Cutting Medicaid to pay for low taxes on the rich is a terrible trade for ...epi.orgFeb 28, 2025 ... ... economic growth and employment stemming from Medicaid change (Chodorow-Reich et al. ... “Long-Term Impacts of Childhood Medicaid Expansions on ...
- Vermont Baby Bonds | Office of the State Treasurervermonttreasurer.gov... economic development, and help young people build their future in Vermont. ... Vermont's pilot builds on this model to strengthen long‑term economic mobility…
- 01
- 02
- 03
- 04
- 05
- 06
- 07
- 08
0 Comments