
Vietnam has quietly positioned itself at the intersection of two powerful global currents: an ageing world that travels for care, and a middle class that treats healthcare as a consumer choice rather than a grim necessity.
The Ministry of Health's draft scheme for 2026–2030 treats medical tourism not as a boutique add-on to the country's travel economy, but as a structured industrial ambition with accreditation targets, geographic clustering and explicit policy levers.
The document, reported by Tuoi Tre News, signals a deliberate shift from incidental foreign patients to an organised, quality-assured service chain.
On This Page
- Vietnam's Medical Tourism Ambition Takes Institutional Shape
- Eight Priority Destinations and Their Strategic Rationale
- Five Service Groups Defining the Clinical Product
- Policy Levers: Visas, Pricing and Insurance Payments
- Standardised Services and the Patient Experience Chain
- Competitive Position Within Southeast Asia's Medical Travel Market
- Risks, Execution Gaps and the Road Ahead
What makes the draft notable is its insistence on drawing a clean line between wellness tourism and medical tourism. Wellness travel sells relaxation, spa rituals and mental reset; medical travel sells diagnosis, surgery, dentistry and rehabilitation wrapped inside a journey.
Vietnamese officials acknowledge the two are commercially intertwined yet argue they demand separate regulatory frameworks, pricing logic and quality controls. That distinction matters enormously for insurers, hospital groups and travel operators now deciding where to deploy capital across Southeast Asia.
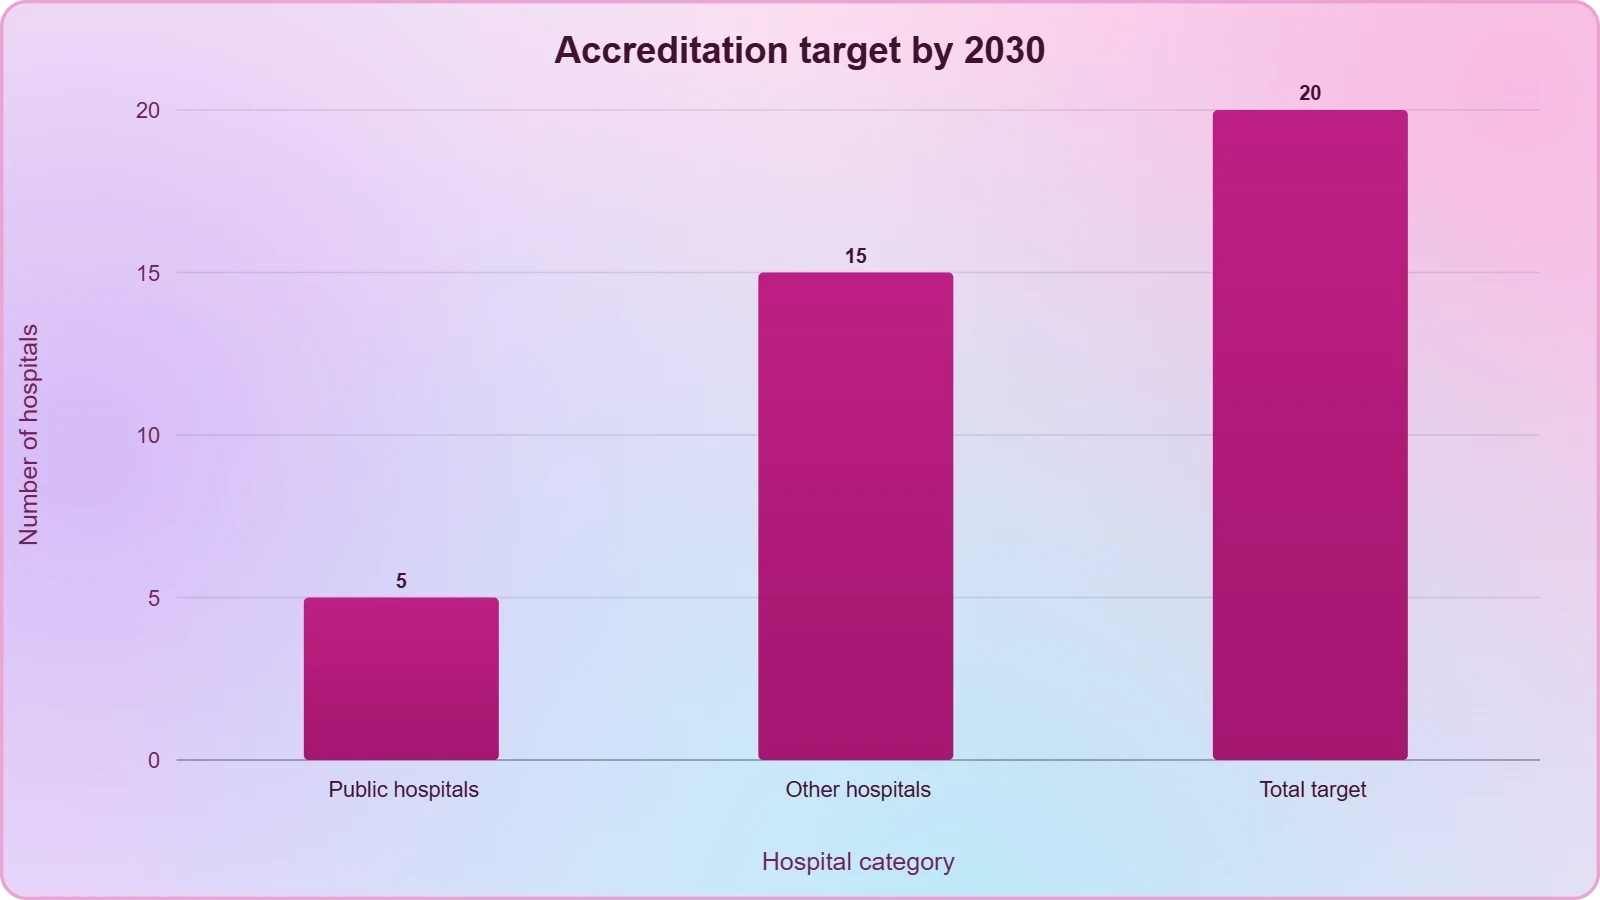
The plan's measurable ambition is concrete: at least twenty hospitals reaching international accreditation by 2030, five of them public. Eight localities are named as priority destinations, from Hanoi and Ho Chi Minh City to Da Nang, Hue, Khanh Hoa and An Giang's Phu Quoc.
Selection rested on healthcare capacity, professional standards, transport links, accommodation depth and demonstrated market demand. The scheme also proposes easier visas, transparent multilingual pricing and international insurance payment channels.
TL;DR Vietnam's Ministry of Health has drafted a 2026–2030 medical tourism scheme aimed at building a professional, safe, high-quality service chain that combines treatment with travel. The plan targets at least twenty internationally accredited hospitals, including five public ones, and names eight priority localities led by Hanoi, Ho Chi Minh City, Da Nang and Phu Quoc. Five service groups are defined, spanning health screening, dentistry and assisted reproduction, specialised treatment, traditional medicine and rehabilitation, plus wellness and elderly care. Supporting measures cover visa facilitation, multilingual pricing transparency, international insurance payments and private investment incentives, all while protecting domestic patients' access to care.
Vietnam's Medical Tourism Ambition Takes Institutional Shape
The draft scheme represents a maturation of Vietnam's healthcare export thinking. Rather than relying on word-of-mouth referrals from diaspora communities or opportunistic hospital marketing, the Ministry of Health is proposing a coordinated national architecture. That architecture links accreditation, destination selection, service standardisation and payment infrastructure into a single policy package.
For a country that already attracts significant dental and cosmetic patients from Australia and the United States, formalisation could convert scattered success into measurable economic value.
The Policy Logic Behind the 2026–2030 Timeline
A five-year horizon gives Vietnam room to build accreditation capacity without rushing hospitals into premature certification. International quality benchmarks such as Joint Commission International or Australian Council on Healthcare Standards require sustained investment in clinical governance, infection control and documentation.
The timeline acknowledges that credibility in medical travel is earned slowly and lost quickly, so the plan prioritises depth of quality over speed of expansion across the designated localities.
Equally important is the economic framing. Officials describe medical tourism as a key economic driver, which places it alongside electronics, textiles and agriculture in the national growth conversation. Healthcare exports generate foreign currency, support high-skill employment and fill hospital capacity during off-peak domestic periods.
The draft implicitly treats medical travel as an export industry whose product happens to be clinical care delivered on Vietnamese soil.
Why Wellness and Medical Tourism Require Separate Frameworks
Wellness tourism thrives on atmosphere, hospitality and sensory experience, with light regulation and low clinical risk. Medical tourism carries surgical risk, informed consent obligations, malpractice exposure and insurance complexity. Merging the two under one policy umbrella would either over-regulate spas or under-regulate operating theatres.
The draft's insistence on differentiated policy reflects a sophisticated understanding of where liability and quality assurance actually sit.
Yet the two sectors share infrastructure. A patient recovering from orthopaedic surgery needs quiet accommodation, nutritious cuisine and gentle movement, all of which wellness resorts already provide. The plan therefore calls for better links between them rather than separation for its own sake.
Hospitals could partner with resort operators for post-operative recovery packages, capturing value that currently leaks to competitors in Thailand and Malaysia.
Eight Priority Destinations and Their Strategic Rationale
The selection of Hanoi, Ho Chi Minh City, Hai Phong, Quang Ninh, Da Nang, Hue, Khanh Hoa and An Giang reveals a deliberate geographic spread. Hanoi and Ho Chi Minh City anchor the plan with tertiary hospitals, specialist expertise and international flight connectivity.
Da Nang and Khanh Hoa contribute resort infrastructure and direct air links to Northeast Asia. Hue brings central Vietnam's traditional medicine heritage, while Phu Quoc in An Giang offers visa-free access and island resort capacity.
Healthcare Capacity as the Primary Filter
Officials weighted professional standards and facilities heavily when choosing destinations. A city cannot host medical travellers without accredited laboratories, imaging equipment, intensive care beds and specialist surgeons. Tourism resources alone would produce attractive but clinically hollow destinations.
The draft therefore embeds a quality-first logic, ensuring that marketing ambition never outruns the actual clinical infrastructure available to foreign patients.
Transport links and accommodation depth complete the filter. Patients often travel with companions who need hotels, restaurants and entertainment during recovery periods. Direct international flights reduce fatigue for post-operative travellers and simplify medical evacuation logistics.
The eight localities collectively satisfy these criteria, though the plan implies differentiated roles rather than uniform development across all sites.
Phu Quoc's Distinctive Positioning
Phu Quoc merits particular attention because it combines island tourism appeal with a special visa regime. The island already hosts international resort brands and receives direct flights from several Asian cities.
Adding accredited medical facilities would allow it to compete for recovery and rehabilitation travellers who want beachside convalescence rather than urban hospital surroundings. That positioning mirrors successful models in Thailand's Phuket and Malaysia's Penang.
The challenge lies in clinical depth. Island hospitals typically lack the specialist breadth of metropolitan centres, so Phu Quoc will likely focus on wellness, rehabilitation and elderly care rather than complex surgery.
The draft's five service groups accommodate this specialisation, allowing different destinations to develop distinct clinical identities within a shared national brand.
Five Service Groups Defining the Clinical Product
The draft organises medical tourism around five service groups, each targeting distinct patient segments and price points. Health screening and early disease detection appeal to affluent travellers seeking preventive diagnostics within short trips. Dentistry and assisted reproduction attract patients facing long waits or high costs at home. Specialised medical examination and treatment covers complex procedures requiring tertiary hospitals and specialist teams.
Traditional Medicine and Rehabilitation as Differentiators
Vietnam's traditional medicine heritage offers a genuine competitive advantage that few regional rivals can replicate authentically. Herbal treatments, acupuncture and therapeutic massage carry cultural credibility, particularly among East Asian patients.
Combined with modern rehabilitation for stroke recovery, orthopaedic recovery and chronic pain, this service group could position Vietnam distinctly from Thailand's cosmetic-led market.
Rehabilitation also aligns naturally with longer stays, which generate higher tourism revenue per patient. A knee replacement patient may spend two weeks in hospital and another three in supervised recovery, during which companions shop, dine and explore.
That extended dwell time multiplies economic impact across accommodation, transport and hospitality sectors far beyond the clinical fee itself.
Wellness, Resort and Elderly Care
Elderly care represents the most commercially significant long-term opportunity within the draft. Japan, South Korea and Australia all face ageing populations with insufficient care capacity and rising costs. Vietnam offers warmer climates, lower labour costs and growing resort infrastructure suited to assisted living. The plan's inclusion of elderly care signals awareness that medical tourism extends well beyond episodic surgical visits.
Resort-based wellness completes the service architecture, capturing travellers who may begin with spa treatments and later graduate to diagnostic screening. This progression model builds familiarity and trust, converting leisure visitors into repeat medical consumers.
The draft's linkage of medical facilities with accommodation, transport and support services formalises what has until now been informal market experimentation.
- 01
- 02
- 03
- 04
Policy Levers: Visas, Pricing and Insurance Payments
Clinical excellence alone does not create a medical tourism industry; friction at the border and at the billing desk can undo years of hospital investment. The draft recognises this by proposing easier visa and accommodation arrangements for international patients and their companions.
Companions matter commercially because they double accommodation and dining spend while providing essential post-operative support to recovering patients.
Transparent Pricing in Multiple Languages
Price opacity is one of the deepest anxieties for medical travellers, who often compare quotes across countries without reliable information. The draft calls for clear information on quality and costs available in multiple languages.
Standardised service pricing covering consultation, booking, reception, treatment, payment and follow-up would allow patients to compare Vietnam against Thailand, Malaysia and Singapore on a like-for-like basis.
Transparency also protects Vietnam's reputation. Hidden charges or unexpected complications billed separately generate damaging online reviews that spread quickly through patient communities. By mandating published pricing and defined service bundles, the plan reduces the risk of individual hospital misconduct damaging the national brand. That collective discipline is essential in a market where trust travels faster than advertising.
International Insurance and Private Investment Incentives
Direct billing arrangements with international insurers would transform Vietnam's accessibility for patients from countries with comprehensive health coverage. Currently, most medical travellers pay out of pocket and seek reimbursement later, which limits the market to affluent individuals. Guidance on international insurance payments could open the door to corporate and expatriate segments with employer-funded coverage.
Incentives for private investment address the capital gap. Accreditation, equipment upgrades and multilingual staffing require substantial funding beyond public budgets. By offering tax or regulatory incentives, the government hopes to attract hospital groups, resort operators and insurance partners into joint ventures. Public hospitals, meanwhile, must meet the five-accreditation target without diverting resources from domestic patients.
Standardised Services and the Patient Experience Chain
The draft's most operationally demanding proposal is the standardisation of the entire patient journey. Consultation, appointment booking, reception, treatment, payment and follow-up care would follow defined protocols with published quality and cost information.
Such end-to-end standardisation is rare in emerging medical tourism markets, where hospitals often excel clinically but stumble on coordination and communication.
Multilingual Communication as a Trust Mechanism
Language barriers generate medical risk and commercial damage simultaneously. A patient who cannot understand discharge instructions may suffer complications; one who cannot understand a bill may broadcast grievances online. Multilingual information covering quality indicators and costs addresses both problems. It also signals professionalism to referring physicians abroad, who act as gatekeepers for many international patient flows.
Follow-up care extends the relationship beyond the trip itself. Remote consultations, shared medical records and coordination with home-country physicians transform a one-off transaction into an ongoing care relationship. That continuity supports repeat visits, referrals and word-of-mouth marketing, all of which reduce customer acquisition costs in a market where reputation is the primary channel.
Protecting Domestic Patients
The Ministry of Health explicitly states that medical tourism must not reduce domestic residents' access to services. This safeguard is politically essential in a country where public hospital overcrowding remains a live concern.
The draft's emphasis on private investment and dedicated international wings suggests a dual-track approach, separating foreign patient facilities from domestic queues wherever feasible.
Yet separation carries risks of its own. A two-tier system can breed resentment and divert scarce specialists toward lucrative foreign patients. The plan's accreditation targets for public hospitals complicate this further, since public institutions serve both populations. Careful scheduling, transparent quotas and ring-fenced revenue reinvestment will determine whether the dual-track model earns public acceptance.
Competitive Position Within Southeast Asia's Medical Travel Market
Vietnam enters a crowded field. Thailand pioneered medical tourism with internationally accredited private hospitals and now attracts over a million medical travellers annually. Malaysia has built a government-backed industry through the Malaysia Healthcare Travel Council.
Singapore competes at the premium end with advanced oncology and cardiology, while India dominates on price for cardiac and orthopaedic surgery. Vietnam's draft must therefore find defensible space rather than imitate incumbents.
Cost Advantage and Quality Perception
Vietnam's cost base sits below Thailand and Singapore but above India for many procedures, creating a middle-market opening. Its challenge is perception: international patients often associate Vietnamese healthcare with lower quality than its clinical outcomes warrant.
Accreditation targets directly address this gap by providing third-party validation that patients and referring physicians can verify independently.
The draft's emphasis on traditional medicine and rehabilitation offers differentiation that price competition cannot erode. Thailand's strength in cosmetic surgery and India's in cardiac care are well established; Vietnam's opportunity lies in recovery, elderly care and integrative medicine. These segments reward cultural authenticity and hospitality quality, areas where Vietnam already performs strongly with leisure travellers.
Lessons From Regional Precedents
Thailand's experience shows that private hospital groups can drive an entire national industry, but also that over-reliance on medical travel exposes providers to external shocks. The COVID-19 pandemic emptied international wards overnight, leaving hospitals with fixed costs and no patients.
Vietnam's plan, by linking medical tourism to domestic capacity and public accreditation, may prove more resilient to such disruptions.
Malaysia's model demonstrates the value of a coordinating council that markets the country abroad while enforcing quality standards at home. Vietnam's draft proposes coordination mechanisms but has not yet specified an institutional home for marketing and quality assurance.
Whether the Ministry of Health retains that role or delegates to a dedicated agency will shape implementation speed considerably.
Risks, Execution Gaps and the Road Ahead
Drafts are declarations of intent, and Vietnam's scheme faces several execution risks that will determine whether it becomes policy or remains paper. Accreditation is expensive and slow, requiring hospital leadership, staff training and documentation systems that many public facilities lack.
The five-public-hospital target is ambitious given competing demands on state budgets and the chronic overcrowding already burdening those institutions.
Balancing Foreign Revenue and Domestic Equity
The equity question will dominate public debate. Every specialist hour devoted to a paying foreign patient is an hour unavailable to a domestic patient in a crowded public system. The draft's safeguard language is necessary but insufficient without enforcement mechanisms.
Transparent reporting on foreign patient volumes, revenue reinvestment and domestic waiting times would build credibility and pre-empt political criticism.
Private investment incentives may partially resolve the tension by expanding total capacity rather than reallocating existing resources. If new private hospitals serve foreign patients while public facilities continue serving domestic ones, the equity conflict diminishes. However, private hospitals often recruit specialists from public institutions, indirectly affecting domestic care quality. Managing that labour market dynamic requires deliberate policy attention.
What Success Would Look Like by 2030
By 2030, success would mean twenty accredited hospitals, a functioning multilingual booking and pricing system, direct insurer billing arrangements and measurable foreign patient growth in the eight priority localities. It would also mean documented evidence that domestic patients have not been disadvantaged. The draft's credibility ultimately rests on whether it delivers both commercial growth and social protection simultaneously.
Vietnam's medical tourism plan is best understood as an attempt to convert latent clinical capability into a structured export industry. The country already possesses capable hospitals, attractive destinations and competitive costs. What it has lacked is coordination, accreditation credibility and payment infrastructure.
The 2026–2030 scheme addresses precisely those gaps, and its fate will reveal how seriously Vietnam intends to compete for the world's medical travellers.
From our network :
- Mobile Learning and VR in English: What Global Evidence Reveals About Effective Language TechnologyA systematic review across 14 countries reveals which language-learning technologies genuinely work. Mobile learning, AI, and VR show measurable benefits when pedagogically integrated. This evidence-based guide helps educators and learners select technology that delivers real return on investment.
- How AI Agents Will Change the Way We Manage Personal FinancesExplore how AI agents are transforming personal finance through automated budgeting, bill payment, and investment management, while examining the critical security protocols and governance frameworks required for safe deployment.
- The Hidden Cost of AI Convenience: Why Over-Permissioned Agents Are a Security Time BombDiscover why AI agents with excessive permissions create dangerous single points of failure, and learn how implementing least privilege principles can protect your organization from exploitation.
- Forbidden Matrix Patterns and Visible Lattice Points: A Geometric DictionaryExplore how multidimensional 0–1 matrices encode geometric truths, linking forbidden patterns to visible lattice points and hypergraph theory, with applications in combinatorics and computational geometry.
- The Final Descent: How ESA Retired the Legendary Cluster Constellation After 24 Years of Space Weather ScienceAfter 24 years mapping Earth’s magnetosphere, ESA’s Cluster mission concluded with a precisely controlled reentry over the South Pacific. This analysis explores the scientific legacy, engineering decisions, and debris mitigation principles behind one of space exploration’s most responsible retirements.
- Committed Mediterranean Precipitation Decline: Why Emissions Cuts Alone Cannot Restore Winter RainsNew NOAA research reveals that Mediterranean winter rains may decline irreversibly even with emissions cuts. Explore the science of committed climate change and regional impacts.
- University Language Proficiency Exams: Why Institutional Tests Demand Different Preparation Than IELTS and TOEFLDiscover why university-specific language proficiency examinations differ fundamentally from IELTS and TOEFL, and learn strategic preparation approaches for institutional assessment success.
- Live Online English Classes for Kids: Do They Actually Reduce Anxiety?A ten-week study reveals that synchronous online English classes can significantly reduce child language anxiety while improving listening and reading skills. Discover what makes these programs effective and how parents can select the right one.
- CISA’s Ten-Advisory Wave: Why Generic Patching Fails in OT and How to Build Product-Specific PlaybooksCISA released ten ICS advisories in one week, exposing critical infrastructure risks. Generic patching fails in OT. Learn to build product-specific remediation playbooks.
RESOURCES
- Resources will be updated soon.
- 01
- 02
- 03
- 04
- 05
- 06
- 07
- 08
0 Comments