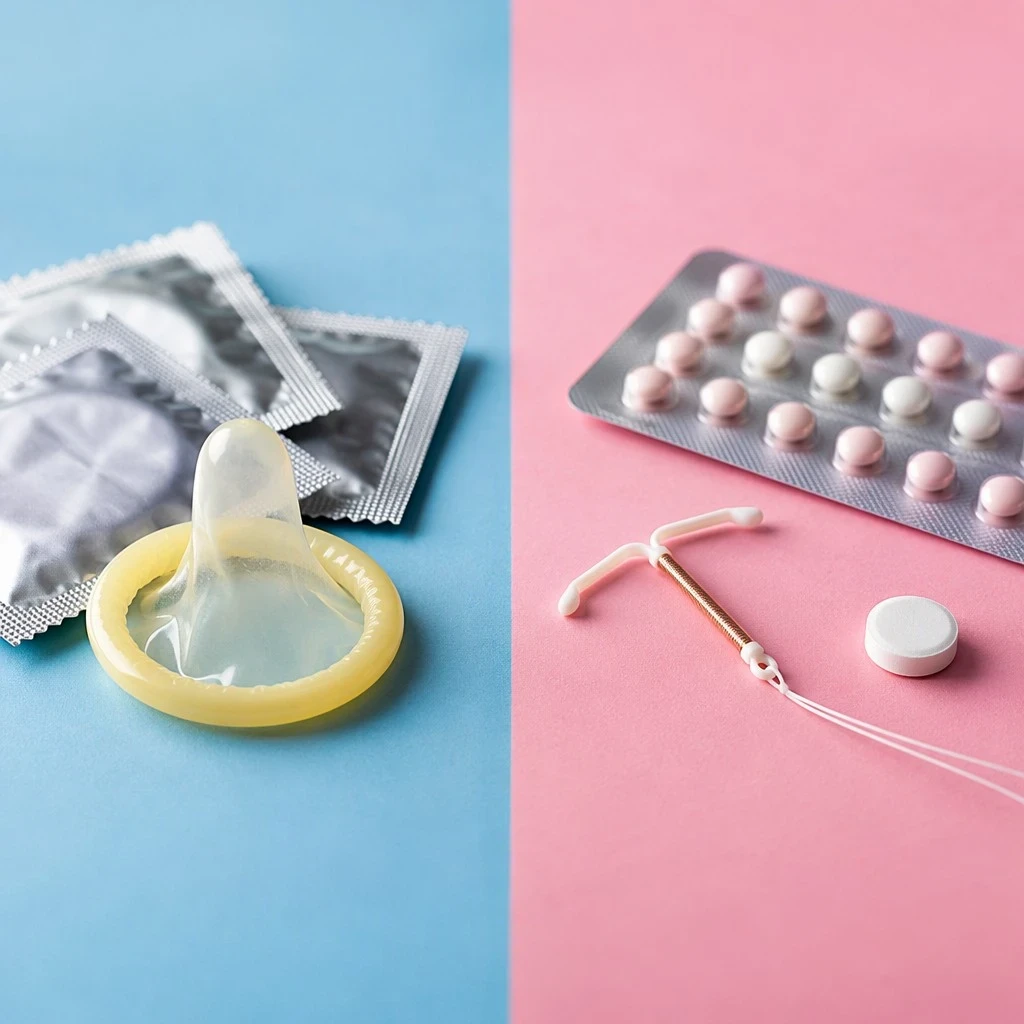
Few decisions in intimate life carry as much quiet consequence as choosing a contraceptive method, and few are surrounded by as much misinformation. Condoms occupy a peculiar position in that landscape: they are the most accessible barrier method on earth, the only one that simultaneously blocks pregnancy and most sexually transmitted infections, and yet they are routinely dismissed as clumsy, unreliable, or merely a stopgap until something "serious" is chosen. That reputation deserves scrutiny rather than repetition, because the evidence tells a more nuanced story about how condoms actually perform when used correctly and consistently.
Comparing condoms with hormonal pills, intrauterine devices, implants, and other barrier options is not a matter of crowning a single winner. Each method trades certain advantages for certain costs, and the right balance depends on a person's health history, relationship circumstances, tolerance for side effects, and appetite for routine. A method that suits one body beautifully can be a poor fit for another, and clinical guidance increasingly reflects that reality by treating contraception as a menu of legitimate choices rather than a hierarchy. What follows is a grounded, evidence-led comparison across the dimensions that matter most.
The analysis below examines effectiveness under typical use rather than laboratory perfection, because real-world behavior is where methods diverge most sharply. It weighs STI protection, convenience, reversibility, hormonal exposure, and cost against one another, and it flags the common myths that distort decision-making. Readers looking for a straight comparison, free of moralizing and free of hype, will find the essential facts organized for practical use.
On This Page
TL;DR Condoms remain the only contraceptive method that also provides meaningful protection against sexually transmitted infections, which makes them uniquely valuable even where hormonal or long-acting methods are more effective at preventing pregnancy. Typical-use failure rates for condoms sit around 13 percent per year, compared with roughly 7 percent for the pill and under 1 percent for implants and IUDs, but those figures assume consistent correct use that many people do not achieve. The strongest strategy is often combination: a highly effective primary method paired with condoms for infection protection. Side effects, cost, reversibility, and personal comfort all legitimately influence the final choice, and no single method is universally superior.
How Contraceptive Effectiveness Is Actually Measured

Contraceptive effectiveness is usually expressed as the number of pregnancies per 100 people using a method for one year, and the distinction between perfect use and typical use is where most public confusion originates. Perfect-use figures describe what happens when a method is followed exactly as directed, while typical-use figures incorporate the forgetfulness, slippage, and timing errors that occur in ordinary life. Reporting only the perfect-use number flatters every method and misleads anyone trying to plan realistically, which is why reputable clinical sources now lead with typical-use data.
The gap between the two figures varies enormously by method. Long-acting reversible contraceptives barely move between perfect and typical use because they remove human error from the equation entirely, whereas methods requiring daily or per-act action show substantial drift. Understanding this asymmetry is the single most useful analytical lens for comparing condoms against pills, patches, rings, and injections, because it explains why a method that looks comparable on paper can perform very differently in practice.
Perfect Use Versus Typical Use
A condom used correctly for every act of intercourse has a first-year failure rate of roughly 2 percent, a figure that reflects the barrier's genuine mechanical reliability when it is intact, correctly sized, and applied before any genital contact. The typical-use rate climbs to about 13 percent, driven largely by inconsistent use rather than product failure. That distinction matters because it locates the problem in behavior and education rather than in the device itself, and it suggests that improving access and instruction could close much of the gap.
Hormonal pills show a similar pattern from a different mechanism. Perfect use yields a failure rate near 0.3 percent, but typical use lands around 7 percent, with missed pills accounting for most of the difference. The pill's advantage over condoms in typical use is real but narrower than its advocates sometimes imply, and it disappears entirely in populations with high adherence. Neither method is inherently "better" in the abstract; each simply fails in different ways and for different reasons.
Why Long-Acting Methods Change the Calculus
Implants and intrauterine devices achieve typical-use failure rates below 1 percent because they eliminate the need for any action at the moment of intimacy. An implant releases progestin steadily for three to five years, and a copper IUD works without hormones for up to a decade. These methods are the most effective reversible options available, and their effectiveness does not depend on memory, discipline, or negotiation with a partner, which is precisely why clinical guidelines increasingly recommend them as first-line choices for anyone who wants reliable, low-effort protection.
That effectiveness advantage comes with tradeoffs that are not trivial. Insertion can be uncomfortable, initial bleeding patterns often change, and removal requires a clinician visit. Some users report cramping or mood changes, and access varies widely by geography and insurance coverage. The point is not that long-acting methods are overrated but that their superiority on the effectiveness axis does not automatically settle the broader question, since contraception is a multi-dimensional decision rather than a single-metric optimization.
The STI Protection Advantage That No Other Method Offers

No hormonal method, implant, or intrauterine device prevents sexually transmitted infections, and this single fact reshapes the entire comparison. Condoms create a physical barrier that reduces transmission of HIV, gonorrhea, chlamydia, trichomoniasis, and, with somewhat lower but still meaningful efficacy, herpes and human papillomavirus. For anyone not in a mutually monogamous relationship with a partner of known status, that protection is not a minor bonus but a distinct health function that no pill can replicate, and it is the reason public health bodies continue to promote condoms even in eras of highly effective long-acting contraception.
The protective effect depends on consistent and correct use, and it is strongest for infections transmitted through fluids rather than skin-to-skin contact. Herpes and HPV can be transmitted from skin not covered by the condom, so protection is partial rather than absolute. Even so, the reduction in risk is substantial and well documented, and dual-method use, meaning a long-acting or hormonal method for pregnancy plus condoms for infection prevention, is widely recommended as the most complete approach for sexually active people at risk.
What Barrier Protection Actually Covers
Laboratory and epidemiological evidence consistently shows that consistent condom use reduces HIV transmission risk by roughly 80 percent or more, and similar reductions apply to gonorrhea and chlamydia. The protection is mechanical and immediate, requiring no waiting period and no prescription, which makes condoms uniquely suited to situations where infection risk is unknown or changing. For casual encounters, new relationships, and any context where a partner's status is uncertain, the barrier function alone justifies the method's continued prominence in sexual health guidance.
Other barrier methods offer partial alternatives. The internal condom provides similar infection protection and can be inserted in advance, though it is less widely available and often more expensive. Diaphragms and cervical caps cover the cervix but leave the vaginal walls exposed, so their STI protection is limited. Spermicides do not protect against infection and may actually increase irritation and risk in some users, which is why they are rarely recommended as a standalone method today.
Dual-Method Use as the Practical Ideal
Combining a highly effective pregnancy-prevention method with condoms captures the strengths of both approaches and is the strategy most consistently endorsed by sexual health organizations. A user on an implant or IUD gains near-perfect pregnancy protection while condoms handle infection risk, and the combination is more forgiving of occasional condom errors because the primary method provides a safety net. The approach does require negotiation and consistent condom availability, but it represents the most complete protection currently available without abstinence.
Dual-method use also addresses a subtle psychological dynamic: when condoms are framed as the sole method, a single lapse feels catastrophic, which can paradoxically increase anxiety and reduce pleasure. When they are framed as one layer of a layered strategy, the stakes of any individual act drop, and adherence often improves. Clinicians who discuss contraception in these terms report better uptake and more honest conversations about what users will actually do rather than what they ideally should do.
Side Effects, Hormones, and What the Body Tolerates

Condoms carry no systemic hormonal load, which is their quietest but most consequential advantage for users who react poorly to synthetic estrogen or progestin. Hormonal methods can bring nausea, breast tenderness, mood shifts, reduced libido, and changes in bleeding patterns, and while most users tolerate them well, a meaningful minority do not. For anyone with a history of migraine with aura, certain clotting disorders, or hormone-sensitive conditions, combined hormonal methods may be contraindicated outright, leaving barrier and long-acting progestin-only options as the realistic alternatives.
Condom side effects are local rather than systemic: latex allergy or sensitivity, irritation from spermicidal lubricants, and occasional discomfort from fit or friction. These are manageable through non-latex materials such as polyisoprene or polyurethane, lubricant selection, and correct sizing. The contrast is instructive, because it illustrates a broader principle in contraceptive counseling: the method with the fewest systemic effects is not automatically the best, but for a subset of users it is the only tolerable one, and that fact deserves more weight than it often receives.
Hormonal Load and Health Contraindications
Combined oral contraceptives are among the most studied medications in history and are safe for the vast majority of users, but their contraindications are real and clinically significant. Estrogen-containing methods raise clot risk modestly, interact with some anticonvulsants and antibiotics, and are generally avoided in smokers over 35. Progestin-only pills, implants, and hormonal IUDs sidestep most of these concerns, though irregular bleeding remains a common reason for discontinuation and a frequent source of frustration for new users.
Barrier methods avoid these considerations entirely, which makes them attractive for people with complex medical histories, those taking interacting medications, and anyone who simply prefers not to alter their hormonal baseline. The tradeoff is that condoms demand per-act attention and offer less pregnancy protection under typical use. Framing the choice as a trade between systemic intervention and behavioral effort is more honest than presenting one path as obviously superior, because the right answer genuinely varies by individual.
Convenience, Cost, and Reversibility
Condoms win decisively on immediacy: no prescription, no appointment, no waiting period, and no clinical procedure. They are available in pharmacies, clinics, and vending machines, often free through public health programs, and they can be started or stopped at any moment without medical supervision. That frictionless quality matters enormously for adolescents, for people in new relationships, and for anyone whose access to healthcare is limited by cost, geography, or confidentiality concerns.
Long-acting methods require an insertion procedure and a removal visit, though their day-to-day convenience is unmatched once in place. The pill demands daily adherence and periodic refills. Cost varies widely by insurance and jurisdiction, and the cheapest option on paper may not be the cheapest in practice once travel, time off work, and repeat prescriptions are counted. Reversibility is another axis: condoms and pills reverse instantly, injections can take months to wear off, and IUDs and implants reverse upon removal.
- 01
- 02
- 03
- 04
We Also Published
Common Myths and the Evidence Behind Them
Condom misinformation is remarkably persistent, and it shapes behavior in ways that measurable data can correct. The claim that condoms reduce sensation so much that they are not worth using is subjective and often overstated; studies comparing condom users with non-users report satisfaction differences that are smaller than popular belief suggests, and lubrication and fit improvements close much of the gap. The claim that condoms fail frequently in laboratory terms is simply false, since breakage rates in correct use are low and most failures trace to incorrect application or reuse.
Another durable myth holds that hormonal methods cause weight gain and infertility, both of which are largely unsupported by the best available evidence. Some users do gain modest weight, but the effect is small and inconsistent across studies, and fertility returns promptly after stopping most methods. Correcting these misconceptions matters because fear of side effects is a leading reason for discontinuation and for reliance on less effective methods, which paradoxically increases both pregnancy and infection risk.
Effectiveness Misconceptions
The most consequential misconception is that condoms are "barely better than nothing," a claim that collapses under scrutiny. A 13 percent typical-use failure rate is far from perfect, but it represents an 85 percent reduction in pregnancy risk compared with no method, and the infection protection is substantial and independent of pregnancy outcomes. Framing condoms as ineffective because they are not the most effective option is a category error, akin to dismissing seatbelts because airbags exist.
Conversely, overconfidence in hormonal methods carries its own risks. A user who believes the pill is nearly foolproof may not use condoms and may not recognize that missed pills, vomiting, and drug interactions can erode protection. Accurate risk perception, rather than optimism about any single method, is the foundation of good contraceptive decision-making, and it argues for clear, specific counseling rather than reassuring generalities.
Pleasure, Negotiation, and Relationship Dynamics
Condom use is as much a social behavior as a clinical one, and negotiation with a partner often determines outcomes more than product characteristics do. Research on sexual health communication consistently finds that explicit discussion before intimacy improves consistent use, while assumptions and silence predict lapses. Programs that teach negotiation skills, rather than simply distributing condoms, show better adherence, which suggests that the behavioral dimension deserves as much attention as the technological one.
Pleasure concerns are legitimate and worth addressing rather than dismissing. Thinner condoms, textured varieties, non-latex materials, and adequate lubrication all improve the experience, and framing condoms as part of intimacy rather than an interruption helps reframe the conversation. The evidence does not support the idea that condoms ruin sex; it supports the idea that poorly fitted, poorly lubricated, or awkwardly introduced condoms do, and those are solvable problems.
Matching the Method to the Person and the Situation
There is no universally correct contraceptive, only a best fit for a particular body, relationship, and stage of life. A person in a new relationship with unknown partner status has different priorities than someone in a long-term mutually monogamous partnership, and a person with a contraindication to estrogen has different options than one without. Effective counseling therefore begins with questions rather than recommendations, exploring health history, pregnancy intentions, infection risk, and tolerance for routine before narrowing the field.
Age and life stage matter as well. Adolescents often benefit from methods that do not require foresight or negotiation, yet they also face the highest infection risk and the greatest access barriers, which makes condoms both essential and insufficient on their own. People approaching menopause may find their needs shift as fertility declines but infection risk persists. Someone who has completed childbearing may prefer a permanent method, while someone planning pregnancy within a year should favor rapid reversibility.
Scenarios and Reasonable Choices
For a new relationship with uncertain infection status, dual-method use with condoms plus a long-acting or hormonal method is the most defensible default, and it can be simplified once both partners have been tested and a mutually monogamous agreement is established. For a person who cannot tolerate hormones, condoms paired with a copper IUD offer strong pregnancy protection without systemic exposure. For someone who struggles with daily adherence, an implant or IUD removes the adherence problem entirely.
For people who have intercourse infrequently, condoms are often the most practical choice because they carry no ongoing cost or hormonal exposure between acts. For those with latex sensitivity, polyisoprene and polyurethane alternatives perform comparably when used correctly. The pattern across all these scenarios is the same: the best method is the one a person will actually use consistently, and consistency depends on fit with real life rather than on theoretical superiority.
Where Condoms Fit in a Modern Strategy
Condoms remain indispensable in any comprehensive sexual health strategy, not because they are the most effective pregnancy preventive but because they are the only widely available method that addresses infection and pregnancy together. Their role has shifted from default to essential component, and that reframing is more accurate than either the old assumption that condoms are the obvious choice or the newer tendency to treat them as an afterthought once a "real" method is chosen.
The most defensible position, supported by clinical guidance and epidemiological evidence, is that condoms belong in almost every sexually active person's toolkit, whether as a primary method, a backup, or a dual-method partner. Treating them as one legitimate option among several, each with distinct strengths and costs, produces better decisions than ranking methods on a single axis. That is the practical conclusion the evidence supports, and it is more useful than any sweeping verdict.
Reading the Comparison Correctly
The comparison between condoms and other contraceptives resolves not into a ranking but into a division of labor. Hormonal and long-acting methods are superior at preventing pregnancy, particularly under typical use, and they deserve their place as first-line options for many users. Condoms are superior at preventing infection and at removing barriers to access, and they deserve their place as a universal component of safer sex rather than a fallback. Recognizing that each method excels on a different axis is the key to using them well.
What the evidence does not support is the dismissal of condoms as obsolete or the elevation of any single method as universally correct. Contraception is a personal health decision shaped by medical history, relationship context, access, and preference, and the best choice is the one that fits a person's actual life rather than an idealized version of it. Readers who take that principle seriously will make better decisions than those who chase a single "best" method, because the question was never which method wins but which combination works.
From our network :
- The Hidden Cost of AI Convenience: Why Over-Permissioned Agents Are a Security Time BombDiscover why AI agents with excessive permissions create dangerous single points of failure, and learn how implementing least privilege principles can protect your organization from exploitation.
- Committed Mediterranean Precipitation Decline: Why Emissions Cuts Alone Cannot Restore Winter RainsNew NOAA research reveals that Mediterranean winter rains may decline irreversibly even with emissions cuts. Explore the science of committed climate change and regional impacts.
- University Language Proficiency Exams: Why Institutional Tests Demand Different Preparation Than IELTS and TOEFLDiscover why university-specific language proficiency examinations differ fundamentally from IELTS and TOEFL, and learn strategic preparation approaches for institutional assessment success.
- Live Online English Classes for Kids: Do They Actually Reduce Anxiety?A ten-week study reveals that synchronous online English classes can significantly reduce child language anxiety while improving listening and reading skills. Discover what makes these programs effective and how parents can select the right one.
- CISA’s Ten-Advisory Wave: Why Generic Patching Fails in OT and How to Build Product-Specific PlaybooksCISA released ten ICS advisories in one week, exposing critical infrastructure risks. Generic patching fails in OT. Learn to build product-specific remediation playbooks.
- Mobile Learning and VR in English: What Global Evidence Reveals About Effective Language TechnologyA systematic review across 14 countries reveals which language-learning technologies genuinely work. Mobile learning, AI, and VR show measurable benefits when pedagogically integrated. This evidence-based guide helps educators and learners select technology that delivers real return on investment.
- The Final Descent: How ESA Retired the Legendary Cluster Constellation After 24 Years of Space Weather ScienceAfter 24 years mapping Earth’s magnetosphere, ESA’s Cluster mission concluded with a precisely controlled reentry over the South Pacific. This analysis explores the scientific legacy, engineering decisions, and debris mitigation principles behind one of space exploration’s most responsible retirements.
- Forbidden Matrix Patterns and Visible Lattice Points: A Geometric DictionaryExplore how multidimensional 0–1 matrices encode geometric truths, linking forbidden patterns to visible lattice points and hypergraph theory, with applications in combinatorics and computational geometry.
- How AI Agents Will Change the Way We Manage Personal FinancesExplore how AI agents are transforming personal finance through automated budgeting, bill payment, and investment management, while examining the critical security protocols and governance frameworks required for safe deployment.
RESOURCES
- Resources will be updated soon.
- 01
- 02
- 03
- 04
- 05
- 06
- 07
- 08
0 Comments