Australia's medicines regulator has cleared the first daily oral tablet form of Wegovy, a decision that quietly redraws the treatment map for obesity and cardiovascular risk across the country. The Therapeutic Goods Administration's approval, announced on a Tuesday, makes Australia one of a small group of markets where patients can now choose a pill instead of a weekly injection. For a nation that has watched GLP-1 demand surge while supply chains strained, the shift from needle to tablet is more than a convenience story. It is a structural change in how chronic weight management may be delivered, priced, and subsidised in the years ahead.
The approval covers four tablet strengths — 1.5mg, 4mg, 9mg and 25mg — and is restricted to people living with obesity or those who need to lower cardiovascular risk, always under a doctor's prescription. Novo Nordisk, the manufacturer, has publicly identified Australia as a priority market for the pill, and the timing aligns with similar clearances in the United States and Europe. Yet the green light is not the finish line. The TGA still must review packaging and production processes to confirm quality standards before the product reaches pharmacy shelves, and no price has been set. The regulatory machinery, in other words, has opened the door but not yet furnished the room.
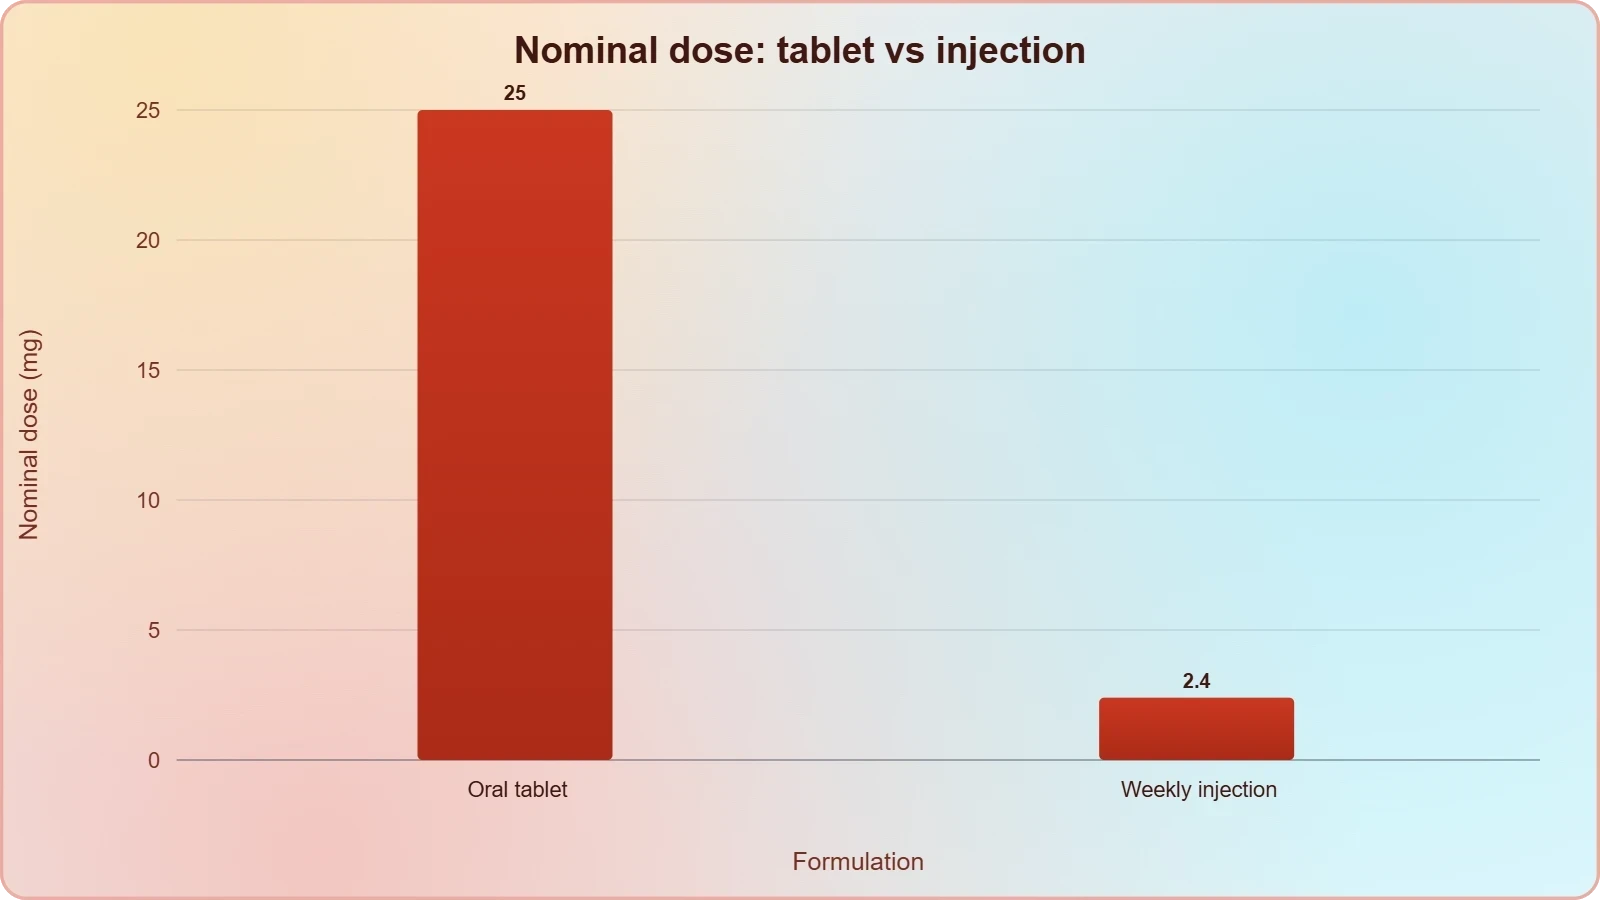
What makes this moment analytically interesting is the economics beneath the headline. Oral semaglutide is absorbed less efficiently than the injected version, so a 25mg tablet is expected to deliver effects comparable to a 2.4mg weekly injection. That absorption gap shapes manufacturing costs, dosing strategy, and ultimately the price patients pay. In the United States, the pill generally costs less than the injection despite carrying more active ingredient per dose, a pricing pattern that defies naive intuition. Australia's Pharmaceutical Benefits Scheme, meanwhile, subsidises weight-loss drugs only for people with type 2 diabetes, leaving most obesity patients to pay out of pocket until policy changes.
On This Page
- The Regulatory Pathway Behind Australia's Oral GLP-1 Approval
- Dosing Science: Why the Pill Needs More Active Ingredient
- Pricing, Subsidy, and the Australian Market Reality
- The Competitive Landscape: Novo Nordisk Versus Eli Lilly
- Public Health Consequences and the Equity Question
- What Comes Next for Patients and Prescribers
TL;DR Australia's TGA has approved the first oral tablet form of Wegovy (semaglutide), a daily GLP-1 pill available in four strengths for obesity and cardiovascular risk reduction. The approval follows US and European decisions and positions Australia as a priority market for Novo Nordisk. Key caveats remain: packaging and production reviews are pending, no price has been set, and the Pharmaceutical Benefits Scheme still subsidises weight-loss drugs only for type 2 diabetes. Oral absorption inefficiency means the 25mg tablet approximates a 2.4mg injection, shaping both clinical dosing and commercial pricing strategy.
The Regulatory Pathway Behind Australia's Oral GLP-1 Approval
The TGA's decision did not emerge from a vacuum. It arrived after regulators in the United States and Europe had already cleared oral semaglutide, creating a body of real-world evidence that Australian assessors could weigh. Regulatory sequencing of this kind is common in pharmaceutical approvals: early movers generate safety and efficacy data, and later jurisdictions benefit from that accumulated record. For Novo Nordisk, the Australian approval represents the third major regulatory pillar in a global rollout strategy, and it signals that the company views the pill as a mainstream product rather than a niche alternative to injections.
What the Approval Actually Permits
The clearance authorises prescription-only use for two distinct populations: people with obesity, and those who need to reduce cardiovascular risk. That second indication matters enormously, because it reframes the drug from a cosmetic-adjacent weight-loss product into a cardiovascular intervention with clinical gravity. The four approved strengths — 1.5mg, 4mg, 9mg and 25mg — give prescribers a titration ladder, allowing gradual dose escalation to manage gastrointestinal side effects that are common with GLP-1 therapies. Patients cannot simply walk into a pharmacy; a doctor's prescription is mandatory, preserving the clinical gatekeeping that regulators consider essential for a chronic-disease medication.
The Unfinished Compliance Steps
Approval and availability are not synonymous. Before the tablet can be released, the TGA must review packaging and production processes to confirm they meet quality standards. This is a routine but consequential step: oral formulations demand tighter control over stability, moisture protection, and bioavailability consistency than injectables, because the gastrointestinal environment is unforgiving. Novo Nordisk has not disclosed a launch timeline, and the company has been contacted for comment. Until those manufacturing reviews conclude, the approval remains a regulatory milestone rather than a commercial reality, and patients should not expect immediate access.
We Also Published
Dosing Science: Why the Pill Needs More Active Ingredient
The most technically revealing detail in the approval is the strength ladder. A 25mg tablet is expected to work like a 2.4mg injection, a roughly tenfold difference in nominal dose that reflects the body's poor absorption of oral semaglutide. The gastrointestinal tract degrades peptides and limits uptake, so manufacturers must load far more active ingredient into each pill to achieve comparable blood concentrations. This absorption penalty is not a flaw in the product; it is a fundamental pharmacokinetic constraint that shapes formulation science, cost structures, and the clinical counselling patients receive when switching from injections.
The Absorption Penalty Explained
Semaglutide is a peptide, and peptides face hostile conditions in the stomach and intestine. Enzymatic degradation and limited membrane permeability mean only a fraction of an oral dose reaches systemic circulation. Novo Nordisk solved part of this problem with an absorption enhancer, sodium N-(8-[2-hydroxybenzoyl] amino) caprylate, commonly abbreviated SNAC, which buffers gastric acid and facilitates uptake across the gastric mucosa. Even so, bioavailability remains low relative to injection. The practical consequence is straightforward: patients swallow a larger milligram quantity to achieve a therapeutic effect that a far smaller injected dose delivers directly into subcutaneous tissue.
Clinical Implications of the Strength Ladder
The four strengths allow gradual titration, which clinicians value because GLP-1 side effects — nausea, vomiting, constipation — are dose-dependent and often transient. Starting low and escalating gives the body time to adapt. For patients transitioning from injections, the equivalence between 25mg oral and 2.4mg injected provides a rough conversion anchor, though individual response varies. Prescribers will need to monitor tolerability carefully, because the oral route introduces variables the injection route avoids: food intake timing, gastric emptying rates, and adherence to daily dosing rather than weekly. A missed weekly injection is a smaller behavioural gap than a missed daily tablet.
Pricing, Subsidy, and the Australian Market Reality
Approval without a price is a promise without a number. Australia has not set a price for the tablet, and the Pharmaceutical Benefits Scheme currently subsidises weight-loss drugs only for people with type 2 diabetes. That policy boundary means the vast majority of obesity patients will pay out of pocket, a financial reality that determines who actually accesses the drug. Novo Nordisk's decision to prioritise Australia suggests confidence in private-market demand, but the absence of subsidy creates an equity question that regulators and policymakers will eventually have to confront as GLP-1 therapies become more central to chronic disease management.
The Subsidy Gap and Who Pays
Australia's PBS restriction is not unusual; many health systems limit public funding for obesity medications, treating them as lifestyle interventions rather than medical necessities. But the cardiovascular indication complicates that framing. If the tablet is prescribed to reduce cardiovascular risk, denying subsidy while funding diabetes treatment creates a clinical inconsistency. Patients with obesity and elevated cardiovascular risk may fall into a gap where the drug is approved but unaffordable. Novo Nordisk has not disclosed Australian pricing intentions, and the company has been contacted for comment. Until a price emerges, the practical reach of this approval remains speculative.
Learning From the American Pricing Pattern
The US experience offers a useful reference point. There, the pill generally costs less than the injection despite containing more active ingredient per dose, a counterintuitive outcome that reflects manufacturing scale, competitive positioning, and payer negotiations rather than raw input costs. Novo Nordisk appears willing to price oral semaglutide aggressively to capture patients who resist injections. In its first five months on the US market this year, the drug received three million prescriptions, a volume that demonstrates substantial pent-up demand for needle-free options. Australia's smaller population will produce different economics, but the direction of pricing pressure is likely similar.
- 01
- 02
- 03
- 04
The Competitive Landscape: Novo Nordisk Versus Eli Lilly
Novo Nordisk is not alone in this arena. Eli Lilly's oral weight-loss drug, Orforglipron, is also awaiting a decision from the TGA, setting up a direct competitive contest in the Australian market. Orforglipron belongs to a different molecular class and may offer distinct dosing or tolerability profiles, though regulatory review will determine how those differences translate into clinical positioning. The presence of a rival oral candidate sharpens Novo Nordisk's incentive to move quickly on pricing and launch logistics, because first-mover advantage in a new format can shape prescribing habits for years.
Orforglipron and the Pending Rival
Eli Lilly's Orforglipron represents a genuine alternative rather than a me-too product. As an oral non-peptide GLP-1 receptor agonist, it sidesteps some of the absorption challenges that force semaglutide tablets to carry large milligram loads. If approved, it could compete on convenience, cost, and possibly tolerability. The TGA's review timeline for Orforglipron remains uncertain, but its pending status means Australian prescribers may soon face a genuine choice between oral options. Competition of this kind typically benefits patients through lower prices and improved access, though it also complicates the clinical decision-making process.
What First-Mover Status Is Worth
Being first in a new delivery format carries tangible commercial value. Prescribers develop habits, patients develop preferences, and pharmacy supply chains orient around the incumbent product. Novo Nordisk's decision to prioritise Australia suggests the company sees strategic value in establishing oral semaglutide before rivals arrive. The three million US prescriptions in five months illustrate how quickly demand can materialise when a needle-free option appears. Whether Australia replicates that trajectory depends on pricing, subsidy decisions, and the speed of the pending manufacturing reviews, all of which remain unresolved.
Public Health Consequences and the Equity Question
Behind the regulatory and commercial layers sits a public health question that Australia, like every wealthy nation, must eventually answer. GLP-1 therapies are effective, but they are expensive, and their benefits concentrate among those who can afford them. When a drug is approved for obesity and cardiovascular risk but subsidised only for diabetes, the health system implicitly rations access by income. That outcome may be fiscally defensible in the short term, but it sits awkwardly beside the clinical evidence showing cardiovascular benefit. The approval therefore raises a policy tension that no pricing announcement can fully resolve.
Who Benefits From Oral Formats
Oral formats expand access in ways that are easy to underestimate. Needle-averse patients, those with dexterity limitations, and people who travel frequently all benefit from a pill that requires no refrigeration and no injection technique. Daily dosing also fits more naturally into existing medication routines for patients already managing multiple tablets. But the format introduces its own adherence risks: a daily pill is easier to forget than a weekly injection, and real-world effectiveness depends on consistent use. The clinical trial data that supported approval assumed disciplined daily dosing, a condition that everyday life rarely guarantees.
The Cost of Leaving Obesity Untreated
Health economists have long argued that the costs of untreated obesity — cardiovascular events, diabetes complications, joint disease, lost productivity — dwarf the price of effective medication. If that calculus holds, restricting subsidy may be a false economy. Australia's decision to approve the tablet without extending subsidy creates a natural experiment: private demand will reveal how many patients are willing to pay, while public health data will show whether untreated obesity continues to burden hospitals. The results of that experiment will inform subsidy debates in the years ahead, and other countries will watch closely.
What Comes Next for Patients and Prescribers
The immediate practical question for Australian patients is timing. Approval has been granted, but packaging and production reviews remain, and no launch date has been announced. Prescribers, meanwhile, must prepare for a new conversation: which patients are suitable for oral therapy, how to titrate safely, and how to counsel on daily adherence. The four-strength ladder gives clinicians flexibility, but it also demands careful patient selection. Those transitioning from injections will need clear guidance on equivalence, and those starting fresh will need realistic expectations about side effects and timelines. The clinical groundwork matters as much as the regulatory milestone.
Practical Guidance for Clinicians
Clinicians should anticipate questions about cost, availability, and comparison with injectable options. Patients will want to know whether the pill works as well, whether it is cheaper, and whether they can switch. The honest answers involve nuance: the 25mg tablet approximates a 2.4mg injection but not perfectly, pricing is undetermined, and switching requires dose recalibration. Prescribers should also flag the daily adherence requirement and the importance of consistent timing relative to food, since oral absorption can be affected by gastric conditions. Documentation of cardiovascular risk factors will matter for patients seeking the broader indication.
The Road Ahead for Australian Policy
Australia now sits within a small group of markets offering oral GLP-1 therapy, and that position carries policy implications. If private demand proves robust, pressure to extend PBS subsidy may build, particularly given the cardiovascular indication. If demand proves modest because of cost, policymakers will face questions about whether approved-but-unaffordable medicines constitute meaningful access. Either way, the TGA's decision marks a starting point rather than an endpoint. The next twelve to twenty-four months will reveal how pricing, competition from Orforglipron, and real-world adherence data reshape the landscape, and other regulators will study the Australian experience closely.
From our network :
- Committed Mediterranean Precipitation Decline: Why Emissions Cuts Alone Cannot Restore Winter RainsNew NOAA research reveals that Mediterranean winter rains may decline irreversibly even with emissions cuts. Explore the science of committed climate change and regional impacts.
- How AI Agents Will Change the Way We Manage Personal FinancesExplore how AI agents are transforming personal finance through automated budgeting, bill payment, and investment management, while examining the critical security protocols and governance frameworks required for safe deployment.
- Live Online English Classes for Kids: Do They Actually Reduce Anxiety?A ten-week study reveals that synchronous online English classes can significantly reduce child language anxiety while improving listening and reading skills. Discover what makes these programs effective and how parents can select the right one.
- University Language Proficiency Exams: Why Institutional Tests Demand Different Preparation Than IELTS and TOEFLDiscover why university-specific language proficiency examinations differ fundamentally from IELTS and TOEFL, and learn strategic preparation approaches for institutional assessment success.
- Forbidden Matrix Patterns and Visible Lattice Points: A Geometric DictionaryExplore how multidimensional 0–1 matrices encode geometric truths, linking forbidden patterns to visible lattice points and hypergraph theory, with applications in combinatorics and computational geometry.
- The Final Descent: How ESA Retired the Legendary Cluster Constellation After 24 Years of Space Weather ScienceAfter 24 years mapping Earth’s magnetosphere, ESA’s Cluster mission concluded with a precisely controlled reentry over the South Pacific. This analysis explores the scientific legacy, engineering decisions, and debris mitigation principles behind one of space exploration’s most responsible retirements.
- Mobile Learning and VR in English: What Global Evidence Reveals About Effective Language TechnologyA systematic review across 14 countries reveals which language-learning technologies genuinely work. Mobile learning, AI, and VR show measurable benefits when pedagogically integrated. This evidence-based guide helps educators and learners select technology that delivers real return on investment.
- The Hidden Cost of AI Convenience: Why Over-Permissioned Agents Are a Security Time BombDiscover why AI agents with excessive permissions create dangerous single points of failure, and learn how implementing least privilege principles can protect your organization from exploitation.
- CISA’s Ten-Advisory Wave: Why Generic Patching Fails in OT and How to Build Product-Specific PlaybooksCISA released ten ICS advisories in one week, exposing critical infrastructure risks. Generic patching fails in OT. Learn to build product-specific remediation playbooks.
RESOURCES
- Resources will be updated soon.
- 01
- 02
- 03
- 04
- 05
- 06
- 07
- 08
0 Comments