The death of Rachel Apa, a 24-year-old product manager from Lewisberry, Pennsylvania, has become one of the most closely examined stories to emerge from the 2026 New York City Marathon. She collapsed roughly three kilometres from the finish line in Central Park while running her first marathon, and despite immediate CPR from a bystander and event medical staff, along with the use of a defibrillator, she could not be saved after being transported to hospital. Her passing has prompted a wider public conversation about the physiological limits of endurance sport, the medical infrastructure that surrounds mass-participation races, and the quiet, deeply personal reasons that compel ordinary people to attempt extraordinary distances.
What distinguishes this case from a routine tragedy is the medical detail her father shared with reporters. Steve Apa told The New York Times that his daughter had rhabdomyolysis, a rare and potentially fatal condition in which skeletal muscle breaks down under extreme exertion and releases proteins and electrolytes into the bloodstream. He described her as having been in good health. That single clinical term has since become the centre of the story, because it reframes a marathon death not as a random cardiac event but as a specific, identifiable, and poorly understood failure mode that endurance athletes and race organisers are only beginning to take seriously.
There is also a human dimension that resists clinical framing. Apa was running to raise money for Parkinson's disease research in honour of her grandfather, who died in 2022, and donations to her fundraising page quickly surpassed its $4,000 target. She had played field hockey in college, worked as an industrial-technology product manager at TE Connectivity, and graduated from Bucknell University. The race itself marked fifty years of the five-borough format and drew a record 61,000 finishers. This analysis examines the medical, organisational, and cultural lessons embedded in her death.
On This Page
TL;DR Rachel Apa, 24, died after collapsing about three kilometres from the New York City Marathon finish line while running her first marathon. Her father reported she had rhabdomyolysis, a rare condition of muscle breakdown under extreme exertion. The case raises urgent questions about endurance-sport physiology, race-day medical readiness, and the culture of pushing through distress. It also documents a young woman running for Parkinson's research in memory of her grandfather, a fundraising effort that exceeded its goal within days of her death.
The Physiology of Exertional Rhabdomyolysis
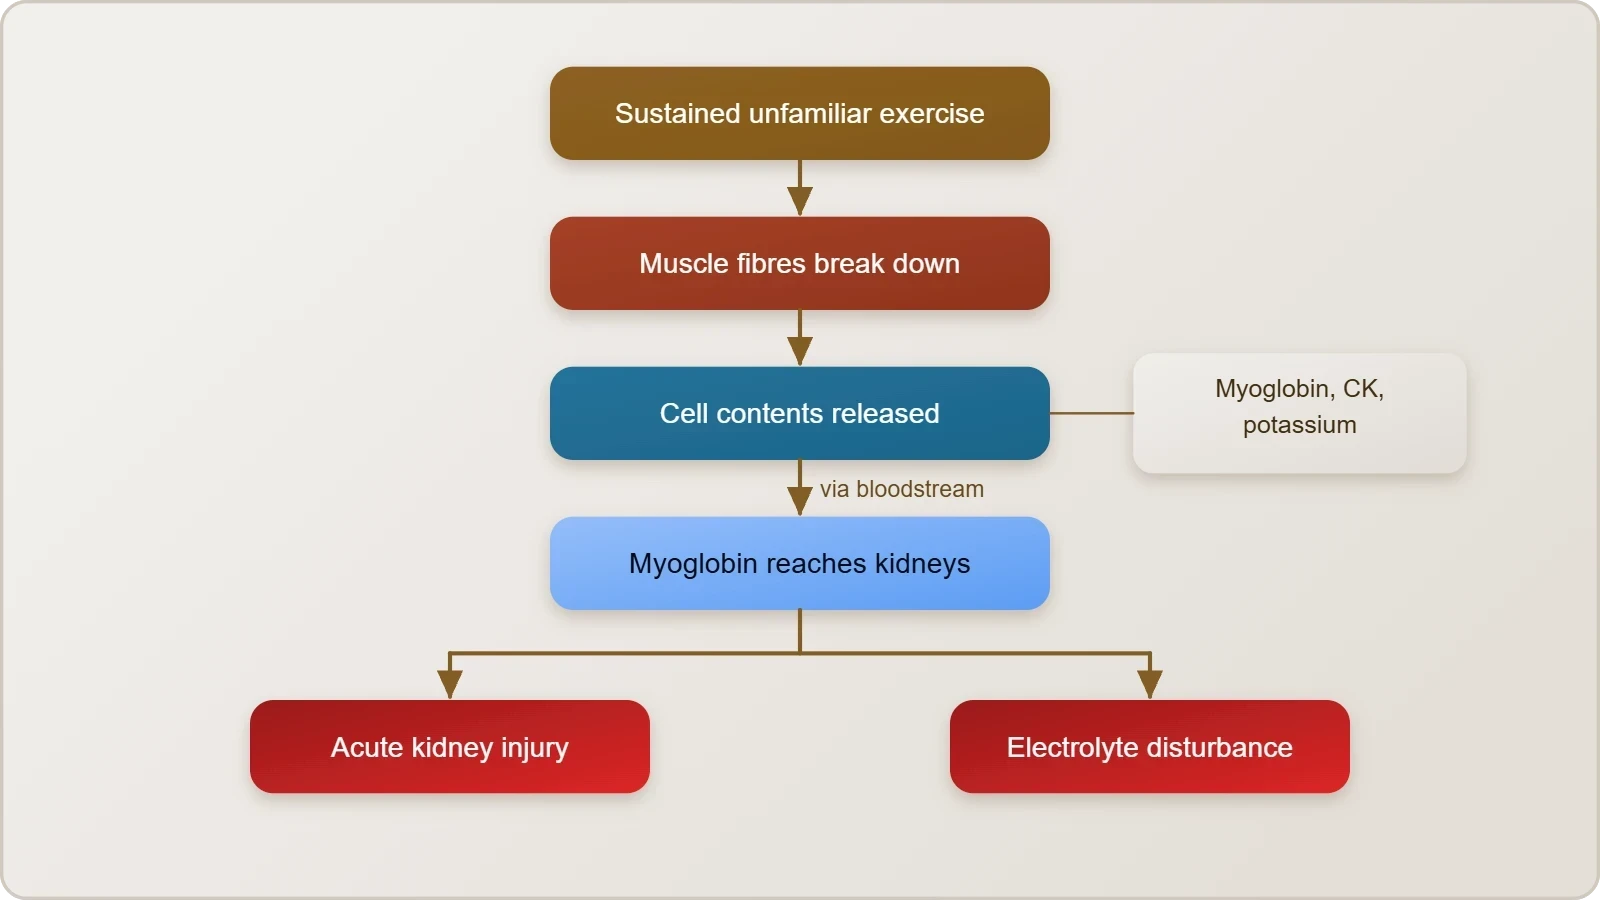
Exertional rhabdomyolysis is a condition in which muscle fibres, subjected to sustained and unfamiliar stress, break down faster than the body can repair them. The damaged cells release myoglobin, creatine kinase, potassium, and other intracellular contents into circulation. In mild cases the body clears these substances without incident; in severe cases the load overwhelms the kidneys, which must filter the myoglobin, and acute kidney injury or dangerous electrolyte imbalance can follow. The condition is rare in recreational runners but not unheard of, and it appears most often when athletes push far beyond their trained capacity.
Why First Marathons Carry Elevated Risk
The marathon distance is uniquely demanding because it sits at the edge of human metabolic endurance. Most runners deplete their stored glycogen somewhere between 30 and 35 kilometres, after which the body increasingly relies on fat oxidation and, in some cases, begins catabolising muscle protein. A first-time marathoner has no prior experience of that physiological wall and may not recognise the difference between ordinary fatigue and the early signals of systemic distress. Training volume, pacing discipline, hydration strategy, and heat exposure all modulate that risk, and none of them can be fully rehearsed before race day.
Rhabdomyolysis is not the only hazard at the far end of a marathon. Hyponatraemia from excessive fluid intake, exertional heat stroke, and sudden cardiac arrest each account for a share of race-day emergencies. What makes rhabdomyolysis distinctive is its subtlety: the onset can be gradual, the symptoms ambiguous, and the collapse sudden. Medical literature consistently notes that early recognition is the decisive factor in outcomes, which places enormous weight on the vigilance of bystanders, volunteers, and medical personnel positioned along the course.
The Clinical Picture and Treatment Window
Once rhabdomyolysis is suspected, the clinical response is aggressive and time-sensitive. Emergency teams typically begin intravenous fluid resuscitation to flush myoglobin through the kidneys, monitor electrolyte levels closely, and watch for signs of compartment syndrome or cardiac arrhythmia. In the field, the priority is rapid transport. The New York case followed that protocol: a bystander and event medical staff performed CPR, a defibrillator was deployed, and paramedics transported the runner to hospital. That the outcome was still fatal underscores how narrow the treatment window can be when muscle breakdown has already progressed.
We Also Published
Race-Day Medical Infrastructure at Scale
The New York City Marathon is among the largest single-day sporting events in the world, and its medical operation reflects that scale. Tens of thousands of runners traverse five boroughs over a course that stretches more than 42 kilometres, and organisers deploy medical tents, mobile response teams, and volunteer clinicians at intervals along the route. The 2026 edition, which marked fifty years of the five-borough format, recorded 61,000 finishers, a figure that magnifies every logistical and clinical challenge. No medical system, however well resourced, can place a clinician within arm's reach of every runner at every moment.
What Bystander Response Revealed
The account provided by Michaela Nicholas, a hospital social worker who witnessed the collapse roughly fifteen metres ahead of her, offers a granular view of how these emergencies actually unfold. She described trying to comfort Apa while two other spectators administered CPR. That detail matters because it shows the response was not solely institutional: ordinary runners and onlookers became the first link in the chain of survival. Bystander CPR and public defibrillator access are the variables most strongly associated with survival in out-of-hospital cardiac events, and their presence in Central Park that day reflects years of public health advocacy.
Yet the case also exposes the limits of that model. CPR and defibrillation address cardiac arrest, but they do not reverse rhabdomyolysis or the metabolic cascade that may precede it. A runner who collapses from muscle breakdown rather than arrhythmia requires a different clinical pathway, one that begins with rapid recognition and intravenous fluids rather than chest compressions alone. The distinction is subtle and rarely discussed outside sports medicine, and it suggests that public and volunteer training could usefully expand beyond cardiac response to include recognition of heat illness, hyponatraemia, and exertional muscle injury.
The Organiser's Duty and the Limits of Waivers
New York Road Runners, the nonprofit that organises the race, expressed deep sadness and offered sympathies to Apa's family, friends, and the running community. That response is standard, but the deeper question concerns institutional responsibility. Race organisers increasingly publish medical protocols, station aid along courses, and require participants to acknowledge risk through waivers. Those measures are meaningful, yet they cannot eliminate the fundamental hazard of asking tens of thousands of people to run a distance that pushes human physiology to its edge. The ethical tension between mass participation and individual safety is not resolvable, only manageable.
The Runner Behind the Headline
Rachel Apa was not a professional athlete, and that is precisely what makes her story resonate. She worked as an industrial-technology product manager at TE Connectivity, a role that suggests a life organised around engineering, deadlines, and quiet competence. She had played field hockey in college, which speaks to a background of team sport and physical discipline, and she graduated from Bucknell University, an institution that issued its own condolences. She was, in other words, the kind of person who takes on a first marathon the way many ambitious young professionals do: as a personal challenge with a purpose attached.
A Fundraising Effort With Personal Roots
That purpose was Parkinson's disease research. Her grandfather died in 2022, and she was running in his honour, raising money through a page that quickly exceeded its $4,000 goal once news of her death spread. The detail transforms the story from a statistical cautionary tale into something more particular. Charity fundraising has become a structural feature of major marathons, with thousands of runners securing entry through philanthropic commitments. It is a system that channels enormous sums toward medical research, and it depends on individuals willing to convert months of training into dollars for causes they carry personally.
The speed with which donations surpassed the goal also reveals something about collective grief in the digital age. Fundraising pages become memorials almost instantly, and strangers contribute as a way of acknowledging a life cut short. That impulse is generous, but it also raises questions about how we process athletic tragedy: the donation is a gesture of solidarity, yet it does not alter the conditions that produced the death. The money will fund research; the questions about endurance-sport safety remain open, and they will not be answered by goodwill alone.
Institutional Condolences and Public Memory
TE Connectivity and Bucknell University both expressed condolences, joining New York Road Runners in acknowledging the loss. These statements are conventional, but they also map the concentric circles of a young adult's life: employer, alma mater, sport, family. In an era when public attention moves quickly, the durability of such tributes depends on whether the institutions follow words with action. A university might fund sports-safety research; an employer might support its employees' athletic pursuits with better health guidance; a race organiser might revisit its medical protocols. Condolences are the beginning of accountability, not its conclusion.
- 01
- 02
- 03
- 04
Risk, Endurance Sport, and the Culture of Pushing Through
Endurance sport carries an implicit cultural message: discomfort is temporary, and the body can be trained to endure more than the mind believes. That message is genuinely empowering, and it is why millions of people run marathons each year. But it also creates a dangerous ambiguity. Runners are taught to distinguish between the pain of effort and the pain of injury, and that distinction is far harder to make in practice than in theory. When a first-time marathoner feels something going wrong at kilometre 39, the social pressure to continue can be immense, and the physiological consequences of ignoring it can be irreversible.
Recognising the Difference Between Fatigue and Failure
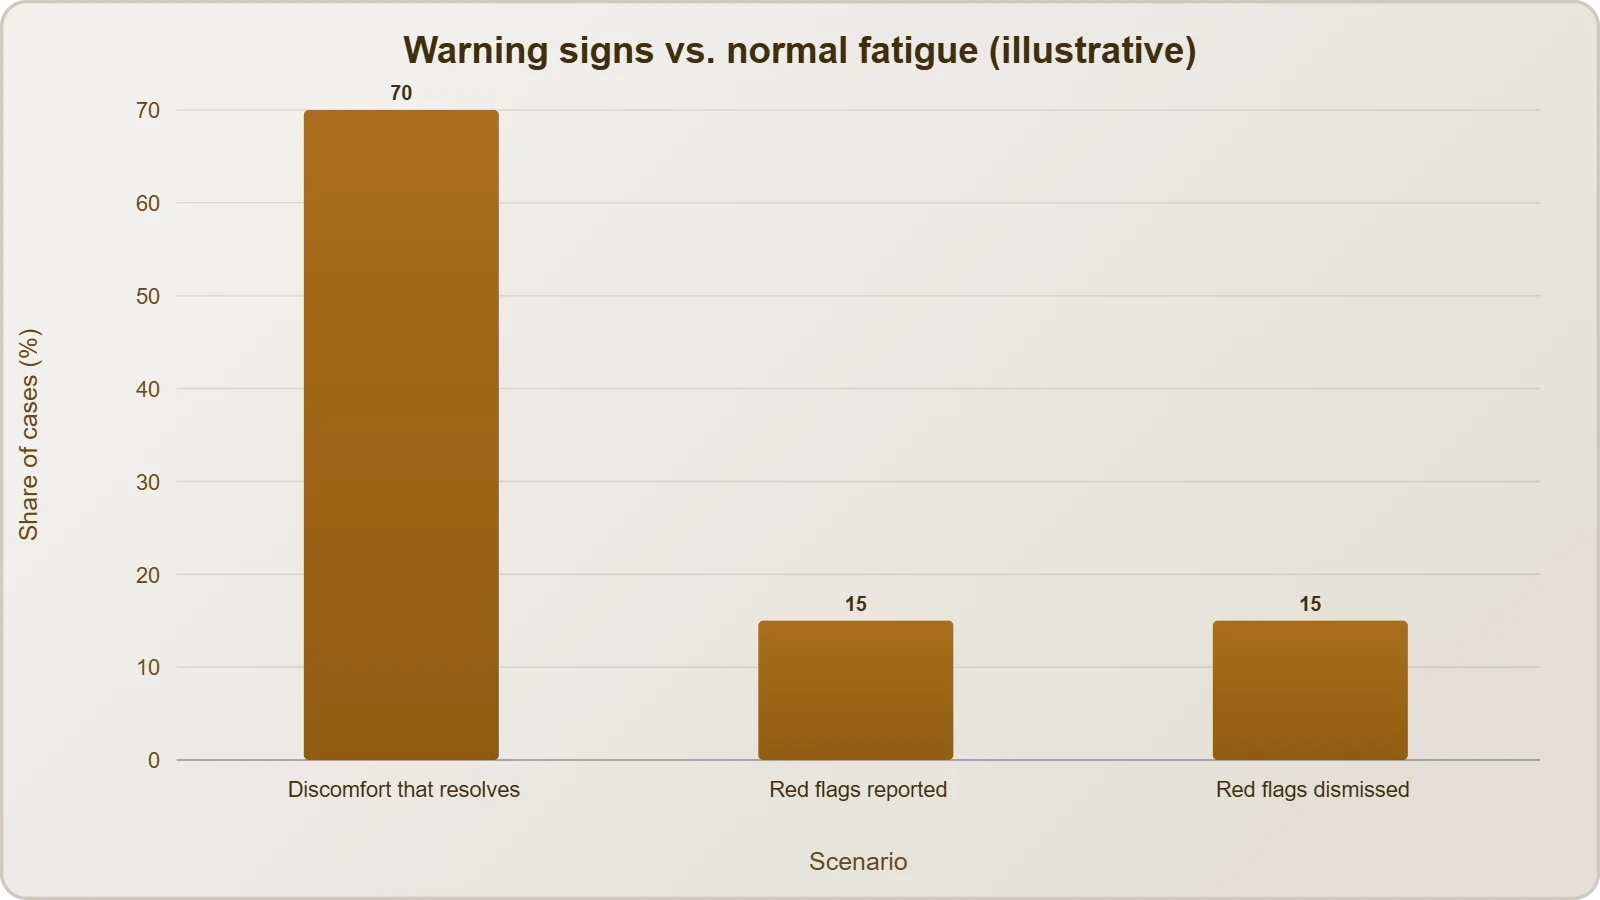
Sports medicine draws a clear line between normal exertional discomfort and warning signs that demand immediate cessation. Cramping that does not resolve, dark urine, confusion, dizziness, and unusual swelling are all red flags. Yet these symptoms often appear late, and a runner in the final kilometres of a marathon is not in an ideal cognitive state to evaluate them. Education campaigns that teach runners to recognise rhabdomyolysis and hyponatraemia before race day could plausibly save lives, and they cost almost nothing to distribute through race registration systems and training apps.
The broader cultural challenge is harder to address. Marathon culture celebrates grit, and stories of runners finishing despite injury are told as inspirational. That narrative has value, but it needs a counterweight: a clear, repeated message that stopping is not failure. Elite athletes withdraw from races when their bodies signal danger, and that decision is treated as professional discipline rather than weakness. Extending the same logic to amateur runners would require a shift in how the sport talks about its own limits, and that shift is already underway in some corners of the running world.
What Race Organisers Can Realistically Change
Organisers cannot eliminate risk, but they can reduce it through design. More frequent medical checkpoints in the final five kilometres, where collapse risk concentrates, would help. So would clearer pre-race communication about the symptoms of exertional illness, mandatory health declarations for first-time marathoners, and better integration of wearable data where runners choose to share it. None of these measures is a panacea, and each carries cost and privacy implications. But the current model, which relies heavily on bystander response and post-collapse intervention, places too much weight on the final link in the chain.
The Medical Examiner's Inquiry and the Search for Cause
The New York City medical examiner's office has said it is investigating the cause of death, a standard procedure that will produce the authoritative account of what happened. Until that report is complete, the public understanding rests on her father's account of rhabdomyolysis and on witness descriptions of the collapse. That gap between anecdote and official finding is uncomfortable but unavoidable. It also matters legally and institutionally: a formal cause-of-death determination shapes insurance claims, potential litigation, and any subsequent changes to race protocols.
Why Official Findings Take Time
Determining cause of death in an exertional collapse requires toxicology, histology, and a review of medical records, and the process can take weeks or months. Investigators must distinguish between primary cardiac events, metabolic causes such as rhabdomyolysis or hyponatraemia, heat illness, and pre-existing conditions that were never diagnosed. Each possibility carries different implications for prevention. A cardiac cause points toward screening and defibrillator access; a metabolic cause points toward hydration strategy, pacing education, and recognition training. The eventual finding will therefore shape the conversation that follows.
There is also a public-interest dimension to how such findings are communicated. Families often want the truth told plainly, while institutions may prefer discretion. In this case, the family has already spoken publicly and with striking candour, which has given the story a specificity that most athletic deaths never receive. That candour is a gift to the running community, because it allows a genuine conversation about a condition that is rarely discussed and poorly understood by most amateur athletes.
Precedent and the Weight of a Single Case
Single cases rarely change systems on their own, but they can catalyse change when they arrive at the right moment. The running boom has produced millions of first-time marathoners, many of whom train with apps and online plans rather than coaches. That population is less likely to have received formal education about exertional illness. If Apa's death prompts even a modest expansion of pre-race health communication, it will have altered the trajectory of the sport. The question is whether the institutions involved will treat the case as a reputational problem to be managed or as a genuine safety signal to be acted upon.
What This Death Means for the Running Community
Every marathon death prompts a period of reflection, and the reflection usually fades. What makes this case different is the specificity of the medical detail, the youth of the runner, and the charitable purpose behind her race. Rachel Apa was running for her grandfather, and the donations that poured in after her death turned a private grief into a public fund for Parkinson's research. That is a small consolation, but it is not nothing. It also places a responsibility on the running community to honour her memory with something more durable than sympathy: better education, better protocols, and a culture that treats stopping as wisdom rather than defeat.
Practical Guidance for Runners and Supporters
Runners preparing for a first marathon should treat hydration and pacing as seriously as mileage. Drinking to thirst rather than to a fixed schedule reduces hyponatraemia risk, and starting conservatively protects against the glycogen depletion that precedes most late-race collapses. Supporters and spectators can learn basic CPR and familiarise themselves with the signs of exertional illness. Race organisers can distribute concise, evidence-based guidance at registration. None of these steps is dramatic, and that is precisely the point: the most effective safety measures in endurance sport are unglamorous, incremental, and widely available.
There is also a case for normalising the decision to withdraw. Runners who stop at kilometre 35 because something feels wrong should be treated as sensible rather than weak, and race results should reflect that stopping is a legitimate outcome. Some events already allow runners to defer entry to a future year if they withdraw for medical reasons, a policy that removes a financial disincentive to stop. Expanding such provisions would cost organisers little and would signal that the sport values its participants' long-term health over a single finish line.
A Legacy Measured in Research Funding
The fundraising page that Apa created will continue to receive donations, and the money will support Parkinson's research in her grandfather's memory. That is a concrete legacy, and it sits alongside the more intangible one: a conversation about rhabdomyolysis that has reached audiences far beyond sports medicine. If even a fraction of the runners who read her story learn to recognise the warning signs, the case will have produced something valuable from something terrible. The running community's response over the coming months will determine whether that potential is realised or allowed to fade with the news cycle.
From our network :
- The Hidden Cost of AI Convenience: Why Over-Permissioned Agents Are a Security Time BombDiscover why AI agents with excessive permissions create dangerous single points of failure, and learn how implementing least privilege principles can protect your organization from exploitation.
- Live Online English Classes for Kids: Do They Actually Reduce Anxiety?A ten-week study reveals that synchronous online English classes can significantly reduce child language anxiety while improving listening and reading skills. Discover what makes these programs effective and how parents can select the right one.
- Committed Mediterranean Precipitation Decline: Why Emissions Cuts Alone Cannot Restore Winter RainsNew NOAA research reveals that Mediterranean winter rains may decline irreversibly even with emissions cuts. Explore the science of committed climate change and regional impacts.
- University Language Proficiency Exams: Why Institutional Tests Demand Different Preparation Than IELTS and TOEFLDiscover why university-specific language proficiency examinations differ fundamentally from IELTS and TOEFL, and learn strategic preparation approaches for institutional assessment success.
- Mobile Learning and VR in English: What Global Evidence Reveals About Effective Language TechnologyA systematic review across 14 countries reveals which language-learning technologies genuinely work. Mobile learning, AI, and VR show measurable benefits when pedagogically integrated. This evidence-based guide helps educators and learners select technology that delivers real return on investment.
- CISA’s Ten-Advisory Wave: Why Generic Patching Fails in OT and How to Build Product-Specific PlaybooksCISA released ten ICS advisories in one week, exposing critical infrastructure risks. Generic patching fails in OT. Learn to build product-specific remediation playbooks.
- How AI Agents Will Change the Way We Manage Personal FinancesExplore how AI agents are transforming personal finance through automated budgeting, bill payment, and investment management, while examining the critical security protocols and governance frameworks required for safe deployment.
- Forbidden Matrix Patterns and Visible Lattice Points: A Geometric DictionaryExplore how multidimensional 0–1 matrices encode geometric truths, linking forbidden patterns to visible lattice points and hypergraph theory, with applications in combinatorics and computational geometry.
- The Final Descent: How ESA Retired the Legendary Cluster Constellation After 24 Years of Space Weather ScienceAfter 24 years mapping Earth’s magnetosphere, ESA’s Cluster mission concluded with a precisely controlled reentry over the South Pacific. This analysis explores the scientific legacy, engineering decisions, and debris mitigation principles behind one of space exploration’s most responsible retirements.
RESOURCES
- Resources will be updated soon.
- 01
- 02
- 03
- 04
- 05
- 06
- 07
- 08
0 Comments